RO-0056
Digital Poster
Filter:
Usefulness of the pedicled latissimus dorsi flap for diverse defective wounds developed in the trunk. RO-0056
Junghyun Lee · Research
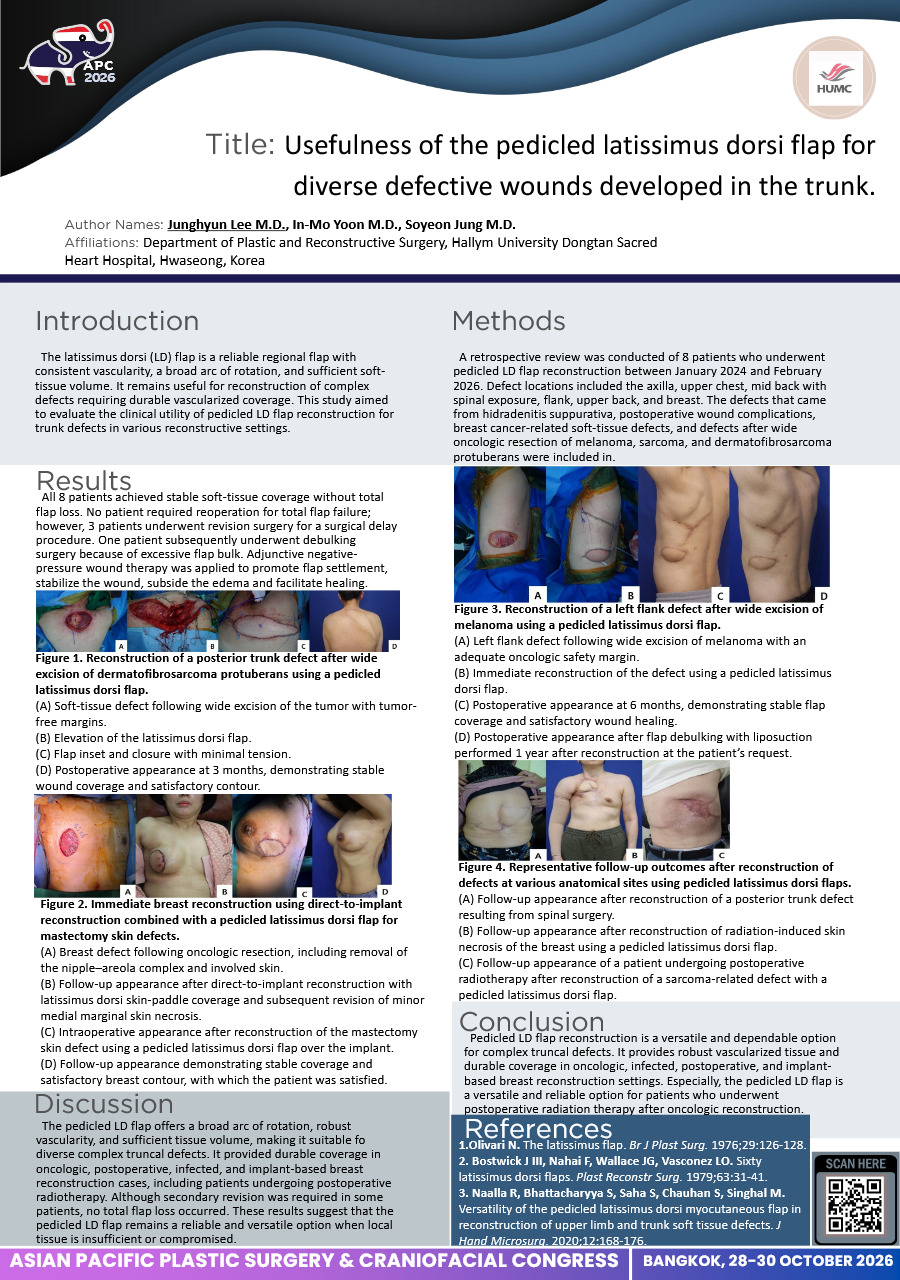
Introduction: The latissimus dorsi (LD) flap is a reliable regional flap with consistent vascularity, a broad arc of rotation, and sufficient soft-tissue volume. It remains useful for reconstruction of complex defects requiring durable vascularized coverage. This study aimed to evaluate the clinical utility of pedicled LD flap reconstruction for trunk defects in various reconstructive settings.
Methods: A retrospective review was conducted of 8 patients who underwent pedicled LD flap reconstruction between January 2024 and February 2026. Defect locations included the axilla, upper chest, mid back with spinal exposure, flank, upper back, and breast. The defects that came from hidradenitis suppurativa, postoperative wound complications, breast cancer-related soft-tissue defects, and defects after wide oncologic resection of melanoma, sarcoma, and dermatofibrosarcoma protuberans were included in.
Results: All 8 patients achieved stable soft-tissue coverage without total flap loss. No patient required reoperation for total flap failure; however, 3 patients underwent revision surgery for a surgical delay procedure. One patient subsequently underwent debulking surgery because of excessive flap bulk. Adjunctive negative-pressure wound therapy was applied to promote flap settlement, stabilize the wound, subside the edema and facilitate healing.
Conclusion: Pedicled LD flap reconstruction is a versatile and dependable option for complex truncal defects. It provides robust vascularized tissue and durable coverage in oncologic, infected, postoperative, and implant-based breast reconstruction settings. Especially, the pedicled LD flap is a versatile and reliable option for patients who underwent postoperative radiation therapy after oncologic reconstruction.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0009
- Title
- Postoperative Retrobulbar Hematoma With Irreversible Visual Loss After Orbital Fracture Reconstruction In An Older Patient
- Author(s)
- Junghyun Lee
- Affiliation
- Department of Plastic and Reconstructive Surgery, Hallym University Dongtan Sacred Heart Hospital, Hwaseong, Korea
Postoperative Retrobulbar Hematoma With Irreversible Visual Loss After Orbital Fracture Reconstruction In An Older Patient CP-0009
Junghyun Lee · Case Study
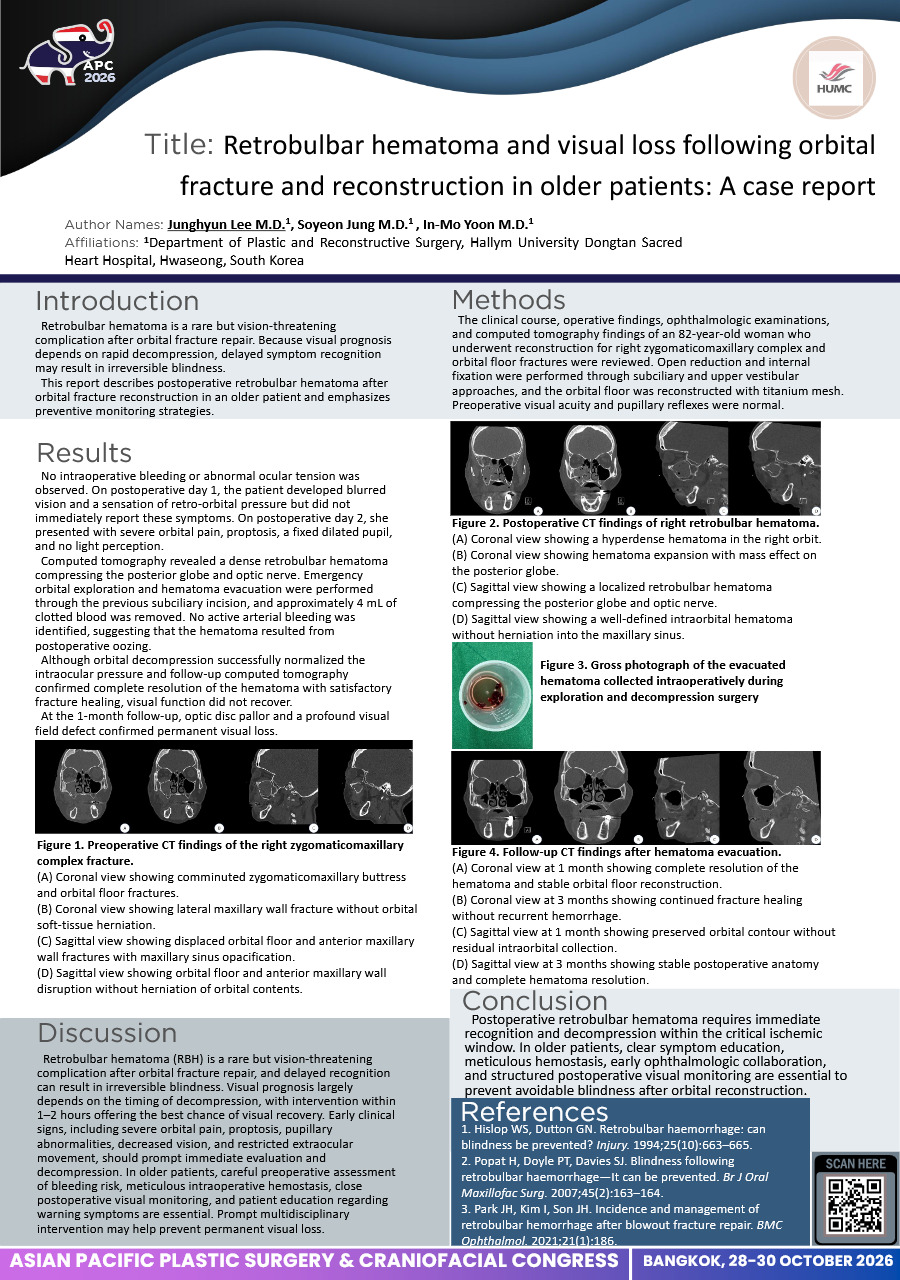
Introduction: Retrobulbar hematoma is a rare but vision-threatening complication after orbital fracture repair. Because visual prognosis depends on rapid decompression, delayed symptom recognition may result in irreversible blindness. This report describes postoperative retrobulbar hematoma after orbital fracture reconstruction in an older patient and emphasizes preventive monitoring strategies.
Methods: The clinical course, operative findings, ophthalmologic examinations, and computed tomography findings of an 82-year-old woman who underwent reconstruction for right zygomaticomaxillary complex and orbital floor fractures were reviewed. Open reduction and internal fixation were performed through subciliary and upper vestibular approaches, and the orbital floor was reconstructed with titanium mesh. Preoperative visual acuity and pupillary reflexes were normal.
Results: No intraoperative bleeding or abnormal ocular tension was observed. On postoperative day 1, the patient developed blurred vision and a sensation of retro-orbital pressure but did not immediately report these symptoms. On postoperative day 2, she presented with severe orbital pain, proptosis, a fixed dilated pupil, and no light perception. Computed tomography revealed a dense retrobulbar hematoma compressing the posterior globe and optic nerve. Emergency orbital exploration and hematoma evacuation were performed through the previous subciliary incision, and approximately 4 mL of clotted blood was removed. No active arterial bleeding was identified, suggesting that the hematoma resulted from postoperative oozing. Although orbital decompression successfully normalized the intraocular pressure and follow-up computed tomography confirmed complete resolution of the hematoma with satisfactory fracture healing, visual function did not recover. At the 1-month follow-up, optic disc pallor and a profound visual field defect confirmed permanent visual loss.
Conclusion: Postoperative retrobulbar hematoma requires immediate recognition and decompression within the critical ischemic window. In older patients, clear symptom education, meticulous hemostasis, early ophthalmologic collaboration, and structured postoperative visual monitoring are essential to prevent avoidable blindness after orbital reconstruction.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0005
- Title
- Modification of Nasoalveolar Molding in a Bilateral Cleft Lip and Palate Patient with a Rotated Premaxilla: A Case Report
- Author(s)
- Thitirath Joongjai
- Affiliation
- Division of Orthodontics, Faculty of Dentistry, Khon Kaen University, Khon Kaen, Thailand
Modification of Nasoalveolar Molding in a Bilateral Cleft Lip and Palate Patient with a Rotated Premaxilla: A Case Report CP-0005
Thitirath Joongjai · Case Study
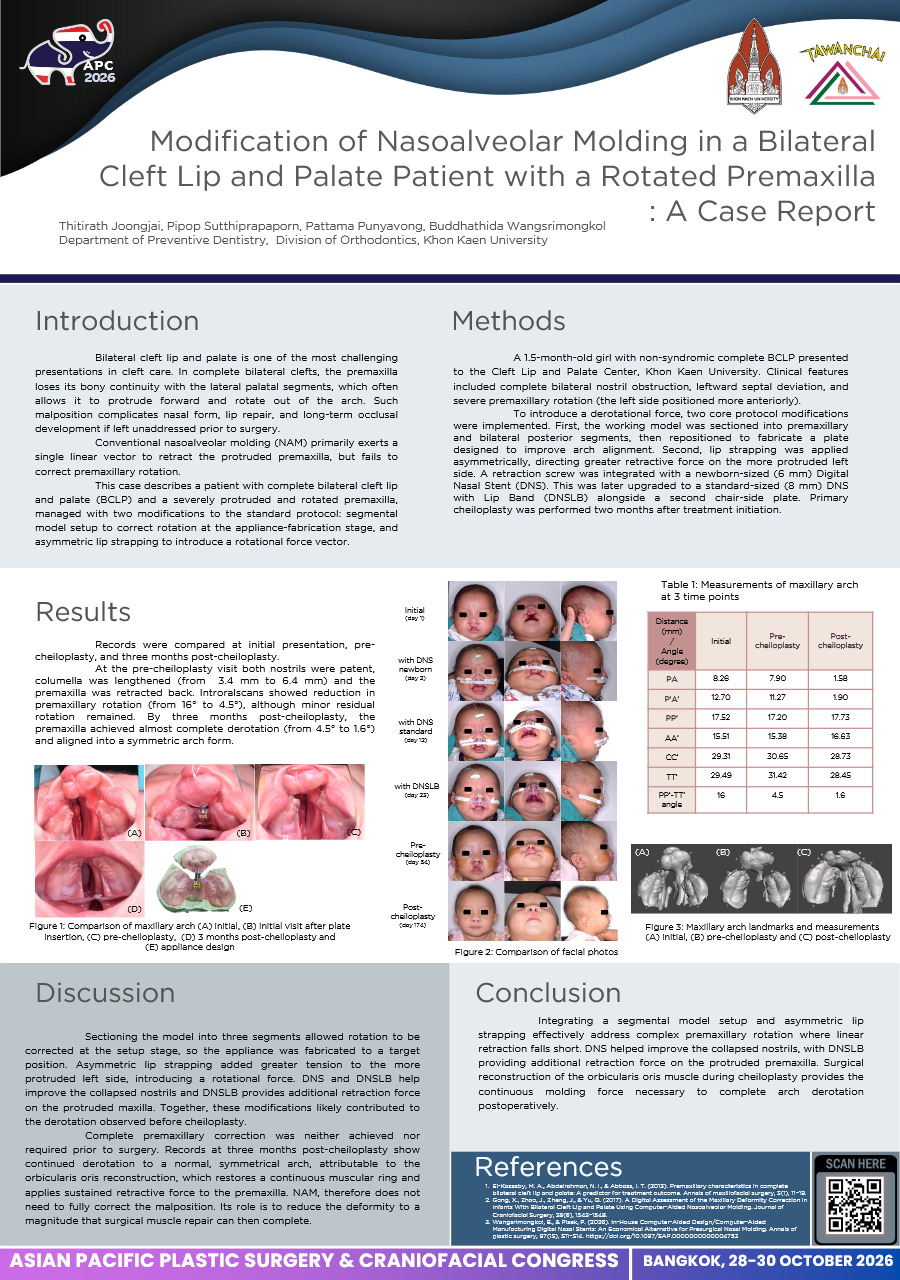
Introduction: Bilateral cleft lip and palate (BCLP) often involves a severely protruded premaxilla lacking bony continuity with the lateral palatal segments. Conventional nasoalveolar molding (NAM) primarily exerts a single linear retraction vector, which fails to correct premaxillary rotation.
Methods: A 1.5-month-old girl with non-syndromic complete BCLP presented to the Cleft Lip and Palate Center, Khon Kaen University. Clinical features included complete bilateral nostril obstruction, leftward septal deviation, and severe premaxillary rotation (left side positioned more anteriorly). To introduce a derotational force, two core protocol modifications were implemented. First, the working model was sectioned into premaxillary and bilateral posterior segments, then repositioned to fabricate a plate targeted to an improved arch alignment. Second, lip strapping was applied asymmetrically, directing greater retractive force on the more protruded left side. A retraction screw was integrated with a newborn-sized (6 mm) Digital Nasal Stent (DNS). This was later upgraded to a standard-sized (8 mm) DNS with Lip Band (DNSLB) alongside a second chair-side plate. Primary cheiloplasty was performed two months after treatment initiation.
Results: Records were compared at initial presentation, pre-cheiloplasty, and three months post-cheiloplasty. Pre-cheiloplasty scans showed reduction in premaxillary rotation with patent nostrils and a lengthened columella, although minor residual rotation remained. By three months post-cheiloplasty, the premaxilla achieved complete derotation and alignment to a symmetrical arch form.
Conclusion: Integrating a segmental model setup and asymmetric lip strapping effectively address complex premaxillary rotation where linear retraction falls short. DNS and DNSLB help improved collapsed nostrils with DNSLB providing additional retraction force on the protruded premaxilla. Surgical reconstruction of the orbicularis oris muscle during cheiloplasty provides the continuous molding force necessary to complete arch derotation postoperatively.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0023
- Title
- A Decade of Cleft Care in Sarawak, Malaysia: A Statewide Registry Review of Cleft Patterns and Surgical Management
- Author(s)
- Daphne Dewi Stephen
- Affiliation
- Hospital Umum Sarawak
A Decade of Cleft Care in Sarawak, Malaysia: A Statewide Registry Review of Cleft Patterns and Surgical Management RP-0023
Daphne Dewi Stephen · Research
Background:
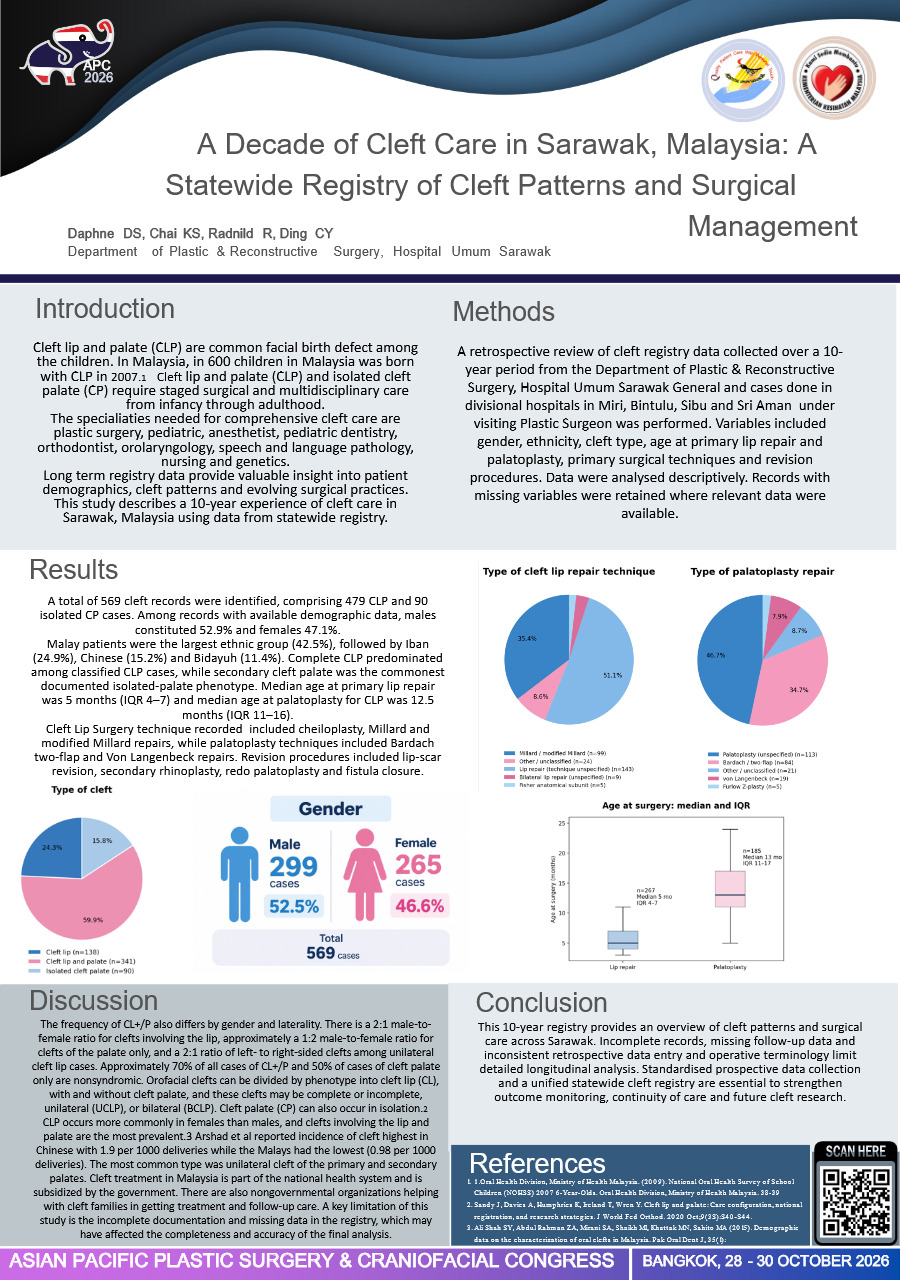
Cleft lip and palate (CLP) and isolated cleft palate (CP) require staged surgical and multidisciplinary care from infancy through adulthood. Long-term registry data provide valuable insight into patient demographics, cleft patterns and evolving surgical practices. This study describes a 10-year experience of cleft care in Sarawak, Malaysia, using data from a statewide cleft registry.
Methods:
A retrospective review of cleft registry data collected over a 10-year period from Sarawak General Hospital/PJS and divisional hospitals in Miri, Bintulu, Sibu and Sri Aman was performed. Variables included gender, ethnicity, cleft type, age at primary lip repair and palatoplasty, primary surgical techniques and revision procedures. Data were analysed descriptively. Records with missing variables were retained where relevant data were available.
Results:
A total of 568 cleft records were identified, comprising 478 CLP and 90 isolated CP cases. Among records with available demographic data, males constituted 52.9% and females 47.1%. Malay patients were the largest ethnic group (42.5%), followed by Iban (24.9%), Chinese (15.2%) and Bidayuh (11.4%). Complete CLP predominated among classified CLP cases, while secondary cleft palate was the commonest documented isolated-palate phenotype. Median age at primary lip repair was 5 months (IQR 4–7) and median age at palatoplasty for CLP was 12.5 months (IQR 11–16). The most common cleft lip procedure technique is Modified Millard Lip repair, while palatoplasty techniques include Bardach two-flap and Von Langenbeck repairs. Revision procedures included lip-scar revision, secondary rhinoplasty, redo palatoplasty and fistula closure.
Conclusion:
This 10-year registry provides an overview of cleft patterns and surgical care across Sarawak. Incomplete records, missing follow-up data and inconsistent retrospective data entry and operative terminology limit detailed longitudinal analysis. Standardised prospective data collection and a unified statewide cleft registry are essential to strengthen outcome monitoring, continuity of care and future cleft research.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0024
- Title
- Reconnecting Cleft Patients to Care: The Role of Combined Cleft Clinics in Strengthening Multidisciplinary Follow-up Across Sarawak, Malaysia
- Author(s)
- Daphne Dewi Stephen
- Affiliation
- Hospital Umum Sarawak
Reconnecting Cleft Patients to Care: The Role of Combined Cleft Clinics in Strengthening Multidisciplinary Follow-up Across Sarawak, Malaysia RP-0024
Daphne Dewi Stephen · Research
Background:
Cleft lip and palate requires coordinated multidisciplinary care extending beyond primary repair into adolescence and adulthood. Patients who default follow-up may miss timely orthodontic treatment, alveolar bone grafting (ABG), or assessment of previous ABG outcomes. A Combined Cleft Clinic was developed in Sarawak to re-engage patients and facilitate coordinated decision-making between Plastic Surgery, Paediatric Dental and Orthodontics.
Methods:
A retrospective review of Combined Cleft Clinics conducted from 2021–2026 at Sarawak General Hospital (SGH), Hospital Miri and Hospital Bintulu was performed. Patients previously under departmental follow-up, including those who had defaulted scheduled care, were reviewed jointly by the multidisciplinary team. Clinic activity, patient attendance and indications for multidisciplinary assessment were evaluated.
Results:
Between 2021 and 2026, 57 Combined Cleft Clinics were conducted, involving 172 patient reviews. SGH conducted 48 clinics involving 142 patients, Hospital Miri conducted eight clinics involving 25 patients, and Hospital Bintulu conducted one clinic involving five patients. Patients with cleft lip and palate were jointly assessed to determine their current treatment requirements. Key decisions included initiation or continuation of orthodontic treatment, assessment of readiness for primary ABG, postoperative evaluation following ABG, and identification of patients requiring redo ABG. The combined clinic enabled simultaneous assessment and consensus treatment planning across surgical, dental and orthodontic specialties, particularly for patients requiring re-establishment of follow-up.
Conclusion:
Combined Cleft Clinics provide an effective platform to reconnect cleft patients with multidisciplinary care while addressing treatment needs that may become apparent following interrupted follow-up. Extending this model beyond the tertiary centre facilitates coordinated decision-making closer to patients across Sarawak. A structured recall system and longitudinal registry are needed to identify patients at risk of defaulting follow-up and maintain continuity of cleft care through adolescence and adulthood.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0008
- Title
- A Standardized Clinical Protocol for Digital Nasal Stents in Patients with Cleft Lip and Palate
- Author(s)
- Pitchaporn Teacharushatakit
- Affiliation
- Khon Kaen University
A Standardized Clinical Protocol for Digital Nasal Stents in Patients with Cleft Lip and Palate RP-0008
Pitchaporn Teacharushatakit · Research
Introduction: Presurgical nasoalveolar molding (NAM) restores nasal symmetry, lengthens the columella, and aligns displaced nasolabial tissues in infants with cleft lip and/or palate (CL/P) prior to primary cheiloplasty. However, traditional manual techniques remain labor-intensive and prone to clinical variability. Advances in computer-aided design and computer-aided manufacturing (CAD/CAM) have facilitated the development of 3D-printed Digital Nasal Stents (DNS) and Digital Nasal Stents with Lip Band (DNSLB). Developed at the Faculty of Dentistry, Khon Kaen University, these appliances offer a standardized, digitally driven alternative to conventional techniques. This report describes a systematic, step-by-step clinical protocol for presurgical nasal molding and postoperative retention using the DNS/DNSLB system.
Methods: Using CAD/CAM technology, two primary 3D-printed appliance series were fabricated: Digital Nasal Stents (DNS) and Digital Nasal Stents with Lip Band (DNSLB), available in three progressive sizes (Newborn, Standard, and Overcorrection). A four-phase clinical protocol was established for sequential presurgical molding and postoperative retention. Treatment initiated at first consultation with the DNS Newborn, combined with lip strapping as needed. At 1–2 weeks, patients transitioned to the DNS Standard alongside an active or passive intraoral plate. Targeted nasal molding was enhanced using the DNSLB Standard before advancing to DNSLB Overcorrection until primary cheiloplasty. Postoperatively (1–2 weeks post-op), appliance sizing was "stepped down" to a DNS Newborn or Standard to mitigate scar contracture and preserve nasal form during healing.
Results: Clinical implementation of the protocol provided a structured, predictable workflow for correcting cleft nasal deformities. Sequential size progression successfully guided alar molding and columellar lengthening presurgically, while postoperative size step-down minimized scar contracture and maintained nasal symmetry throughout healing.
Conclusion: The Khon Kaen University DNS/DNSLB protocol establishes a systematic, digitally driven approach to presurgical nasal molding and postoperative retention. By replacing manual modifications with standardized CAD/CAM progressions, this protocol offers a practical, highly reproducible clinical solution.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0029
- Title
- Survey of chief complaints in patients with cleft lip and/or palate with jaw deformity
- Author(s)
- Natsuko Uchino
- Affiliation
- Department of Oral-Maxillofacial Surgery and Orthodontics,The University of Tokyo Hospital
Survey of chief complaints in patients with cleft lip and/or palate with jaw deformity RP-0029
Natsuko Uchino · Research
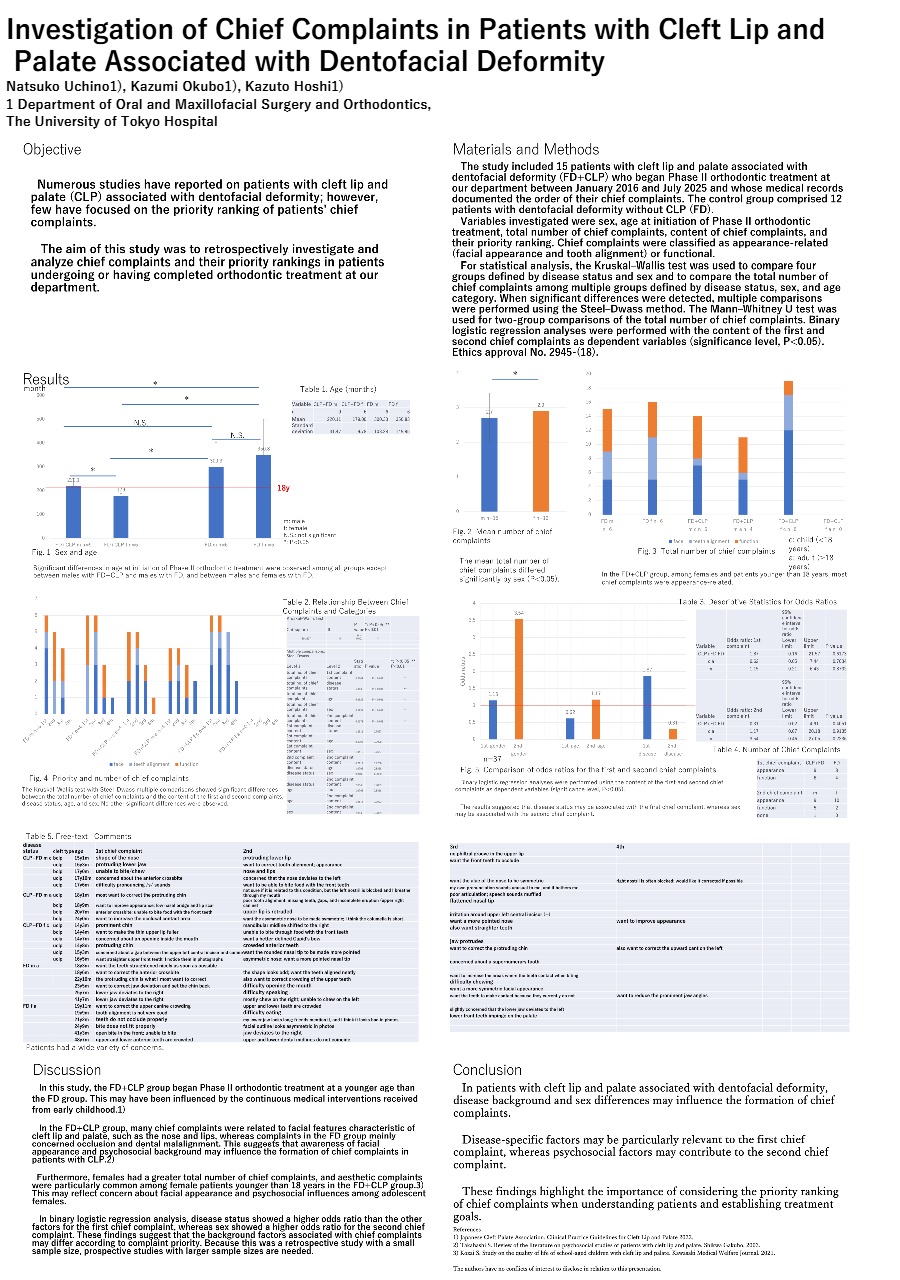
Objective: This study aimed to retrospectively evaluate the content and priority of chief complaints in patients with cleft lip.
Materials and Methods: Fifteen patients with cleft lip and palate accompanied by jaw deformities (FD+CLP) who initiated second-phase orthodontic treatment at our department between January 2016 and July 2025 and had clearly recorded chief complaints were included. Twelve patients with jaw deformities without cleft lip and palate (FD) were enrolled as a control group. The variables analyzed were sex, age at the start of second-phase treatment, total number of chief complaints, and the content and priority of complaints. Chief complaints were classified as esthetic (“appearance”) or functional.
Kruskal–Wallis tests were used for four-group comparisons based on disease and sex and for multigroup comparisons combining disease, sex, and age category, followed by Steel–Dwass multiple comparisons when significant differences were detected. Mann–Whitney U tests were applied for two-group comparisons of the total number of complaints. The significance level was set at P<0.05.
Results: Patients in the FD+CLP group were significantly younger than those in the FD group at the start of second-phase treatment, and within the FD+CLP group, males were significantly older than females (P<0.05). The total number of chief complaints was significantly greater in females than in males (P<0.05), and significant differences were observed among multigroup(P<0.01). Logistic regression analyses suggested that disease was most strongly associated with the content of the first chief complaint (OR 1.9), whereas sex was most strongly associated with the content of the second chief complaint (OR 3.6).
Conclusions: Factors associated with chief complaints differed according to their priority. Disease was associated with the first chief complaint, whereas sex was associated with the second. Further prospective studies with larger sample sizes are warranted.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0009
- Title
- Duration of Presurgical Orthodontic Preparation for Alveolar Bone Grafting in Unilateral Cleft Lip and Palate: Comparison of Clear Aligner, Removable Appliance, and Quad Helix
- Author(s)
- Krisadi Phannarus
- Affiliation
- Queen Sirikit National Institute of Child health
Duration of Presurgical Orthodontic Preparation for Alveolar Bone Grafting in Unilateral Cleft Lip and Palate: Comparison of Clear Aligner, Removable Appliance, and Quad Helix RP-0009
Krisadi Phannarus · Research
Introduction (background and objective):
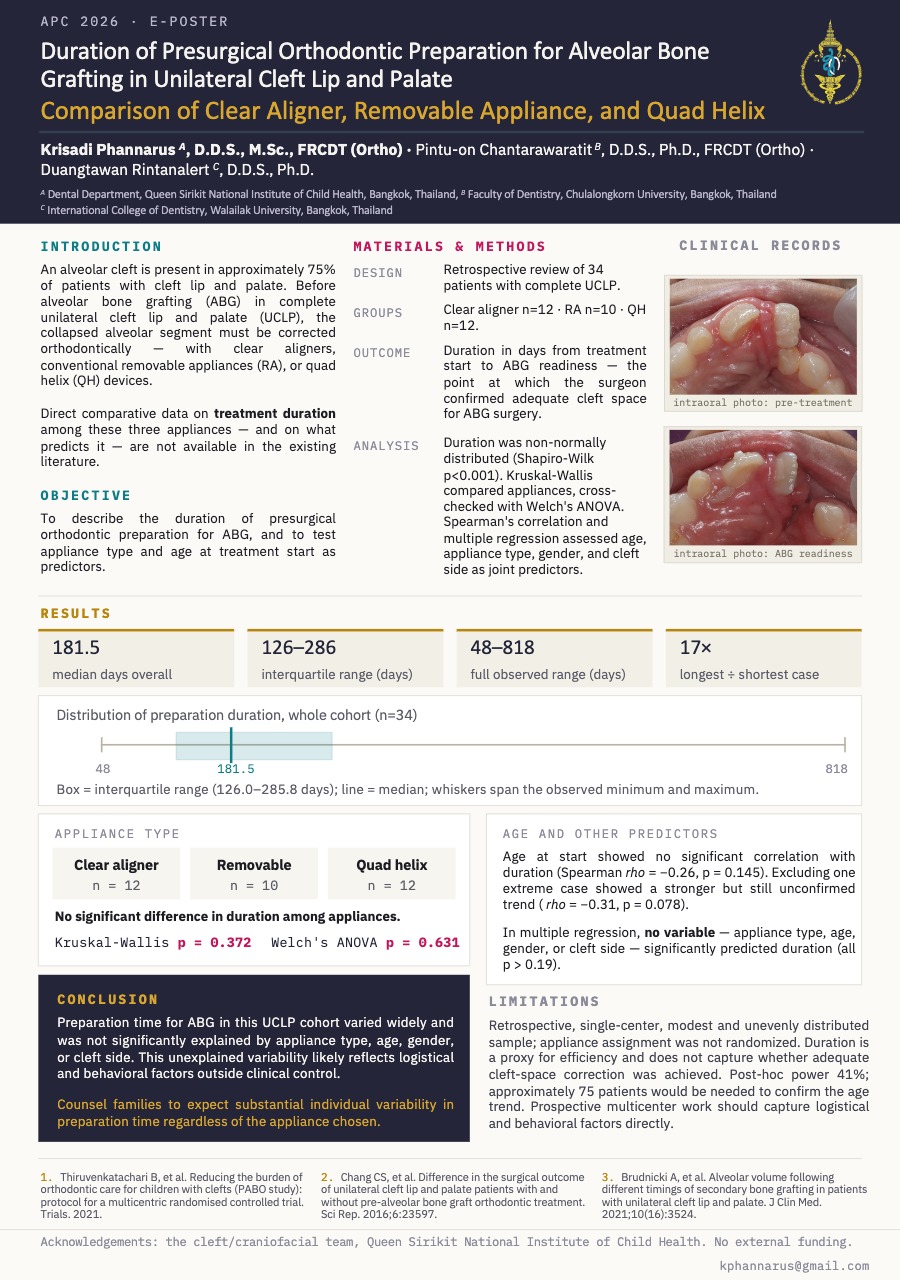
Presurgical orthodontic correction of the collapsed alveolar segment is required before alveolar bone grafting (ABG) in patients with complete unilateral cleft lip and palate (UCLP). Clear aligners, conventional removable appliances (RA), and quad helix (QH) devices are all used for this purpose, but comparative data on treatment duration are limited, making it difficult to counsel families on expected timelines. This study described the duration of presurgical orthodontic preparation for ABG in UCLP patients and compared this duration among clear aligner, RA, and QH groups.
Materials & Methods:
A retrospective review of 31 UCLP patients who underwent presurgical orthodontic treatment before ABG was conducted (clear aligner, n = 11; RA, n = 10; QH, n = 10). The primary outcome was treatment duration (days) from orthodontic treatment initiation to surgeon-confirmed readiness for secondary alveolar bone grafting. Data normality was assessed using the Shapiro–Wilk test, and homogeneity of variances was evaluated using Levene's test. Because the assumption of equal variances was violated, treatment duration among the three groups was compared using Welch's ANOVA, followed by Games–Howell post hoc pairwise comparisons.
Result(s):
Mean treatment duration was 231 ± 93 days for the clear aligner group, 201 ± 100 days for the QH group, and 400 ± 292 days for the RA group. Welch's ANOVA showed no significant difference in treatment duration among the three appliance groups (p = 0.165), and Games–Howell post hoc comparisons were not significant (all p > 0.05).
Conclusion:
No appliance demonstrated significantly faster presurgical preparation for ABG despite numerical differences favoring quad helix. Given wide individual variability, likely influenced by operating-room scheduling, patient cooperation, and laboratory turnaround, clinicians should counsel UCLP families to expect a variable, often prolonged, preparation period and closely monitor canine eruption throughout, regardless of appliance chosen.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0011
- Title
- Clear Aligner Therapy as Presurgical Orthodontic Preparation for Alveolar Bone Grafting in Bilateral Cleft Lip and Palate: A Case Report
- Author(s)
- Pran Pitaksanurat
- Affiliation
- Department of Orthodontics, Faculty of Dentistry, Khon Kaen University, 40002, Thailand / Department of Orthodontics, College of Dental Medicine, Rangsit University, Pathum Thani, 12000, Thailand
Clear Aligner Therapy as Presurgical Orthodontic Preparation for Alveolar Bone Grafting in Bilateral Cleft Lip and Palate: A Case Report CP-0011
Pran Pitaksanurat · Case Study
Introduction
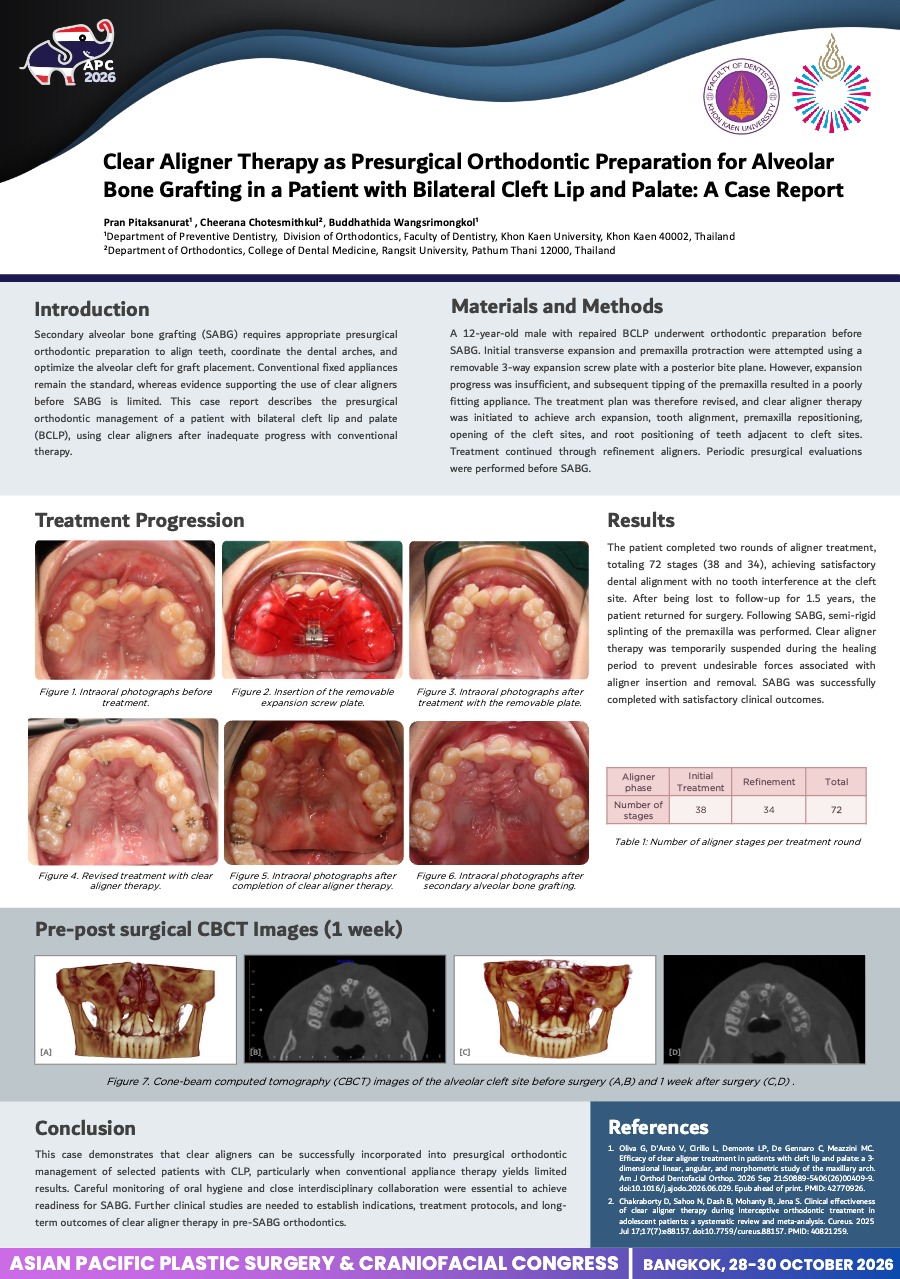
Secondary alveolar bone grafting (SABG) requires presurgical orthodontic preparation to coordinate dental arches, correct transverse deficits, align teeth, and position roots adjacent to the cleft site. Traditionally, this preparation relies on a multistage approach involving palatal expansion followed by fixed appliances. However, evidence supporting the use of clear aligner before SABG remains limited. This case report describes presurgical orthodontic management using clear aligners in a patient with bilateral cleft lip and palate (BCLP) after conventional expansion therapy yielded inadequate progress.
Materials and Methods
A 12-year-old male with repaired BCLP underwent presurgical orthodontic preparation before SABG. Initial transverse expansion and premaxillary protraction were attempted using a removable 3-way expansion screw plate with a posterior bite plane. Expansion was inadequate, and severe premaxillary tipping resulted in poor appliance fit. Rather than transitioning to fixed appliances, treatment was revised to clear aligners to achieve arch expansion, tooth alignment, premaxillary repositioning, cleft-site opening, and root uprighting adjacent to the clefts. Periodic presurgical evaluations were performed.
Results
The patient completed 2 rounds of aligner therapy comprising 72 stages (38 and 34), achieving satisfactory dental alignment and arch coordination for SABG. After a 1.5-year loss to follow-up, the patient returned for surgery. Following SABG, the premaxilla was semi-rigidly splinted, and aligner therapy was temporarily suspended during healing to prevent jiggling forces from aligner insertion and removal. SABG was completed successfully with satisfactory clinical outcomes.
Conclusion
This case demonstrates that clear aligners can be incorporated into presurgical orthodontic management of selected patients with BCLP when conventional appliance therapy yields limited results. Strict oral hygiene and interdisciplinary coordination were essential for graft readiness and postsurgical stability. Further studies are needed to establish indications, treatment protocols, and long-term outcomes of clear aligner therapy before SABG.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0004
- Title
- Pre-Surgical Infant Orthopedic with Digital Nasal Stents and Sequential Alveolar Aligners in Unilateral Complete Cleft Lip and Palate: A Case Report
- Author(s)
- Pornpat Butpun
- Affiliation
- Division of Orthodontics, Faculty of Dentistry, Khon Kaen University, Khon Kaen, Thailand
Pre-Surgical Infant Orthopedic with Digital Nasal Stents and Sequential Alveolar Aligners in Unilateral Complete Cleft Lip and Palate: A Case Report CP-0004
Pornpat Butpun · Case Study
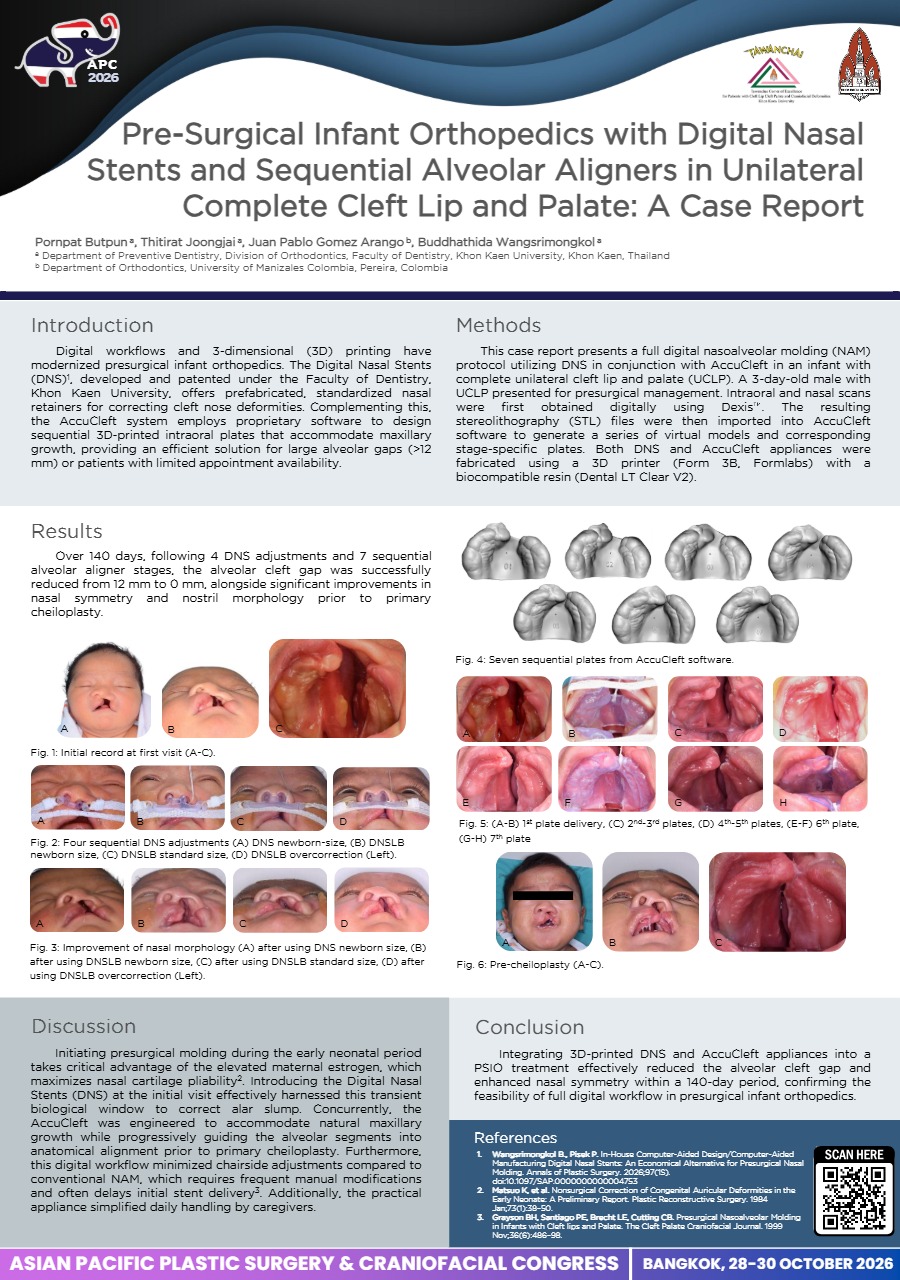
Introduction: Digital workflows and 3-dimensional (3D) printing have modernized presurgical infant orthopedics. The Digital Nasal Stents (DNS), developed and patented under the Faculty of Dentistry, Khon Kaen University, offers prefabricated, standardized nasal retainers for correcting cleft nose deformities. Complementing this, the AccuCleft system employs proprietary software to design sequential 3D-printed intraoral plates that accommodate maxillary growth, providing an efficient solution for large alveolar gaps (>12 mm) or patients with limited appointment availability.
Methods: This case report presents a fully digital nasoalveolar molding (NAM) protocol utilizing DNS in conjunction with AccuCleft in an infant with complete unilateral cleft lip and palate (UCLP). A 3-day-old male with complete UCLP presented for presurgical management. Intraoral impressions and nasal scans were first obtained digitally using Dexis™. The resulting stereolithography (STL) files were then imported into AccuCleft software to generate a series of virtual models and corresponding stage-specific plates. Both DNS and AccuCleft appliances were fabricated using a 3D printer (Form 3B, Formlabs) with a biocompatible resin (Dental LT Clear V2).
Results: Over 140 days, following 4 DNS adjustments and 7 sequential alveolar aligner stages, the alveolar cleft gap was successfully reduced from 12 mm to 0 mm, alongside significant improvements in nasal symmetry and nostril morphology prior to primary cheiloplasty.
Conclusion: Integrating 3D-printed DNS and AccuCleft appliances into a digital NAM workflow effectively eliminated the alveolar cleft gap and enhanced nasal symmetry within a 140-day treatment window, confirming the feasibility of fully digital workflows in presurgical infant orthopedics management.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RO-0077
- Title
- Cross-Linguistic Nasalance Profiles in Healthy Malaysian Adults: A Comparison Across Malay, Mandarin, and Tamil
- Author(s)
- Hasherah Mohd Ibrahim
- Affiliation
- UNIVERSITI KEBANSAAN MALAYSIA
Cross-Linguistic Nasalance Profiles in Healthy Malaysian Adults: A Comparison Across Malay, Mandarin, and Tamil RO-0077
Hasherah Mohd Ibrahim · Research
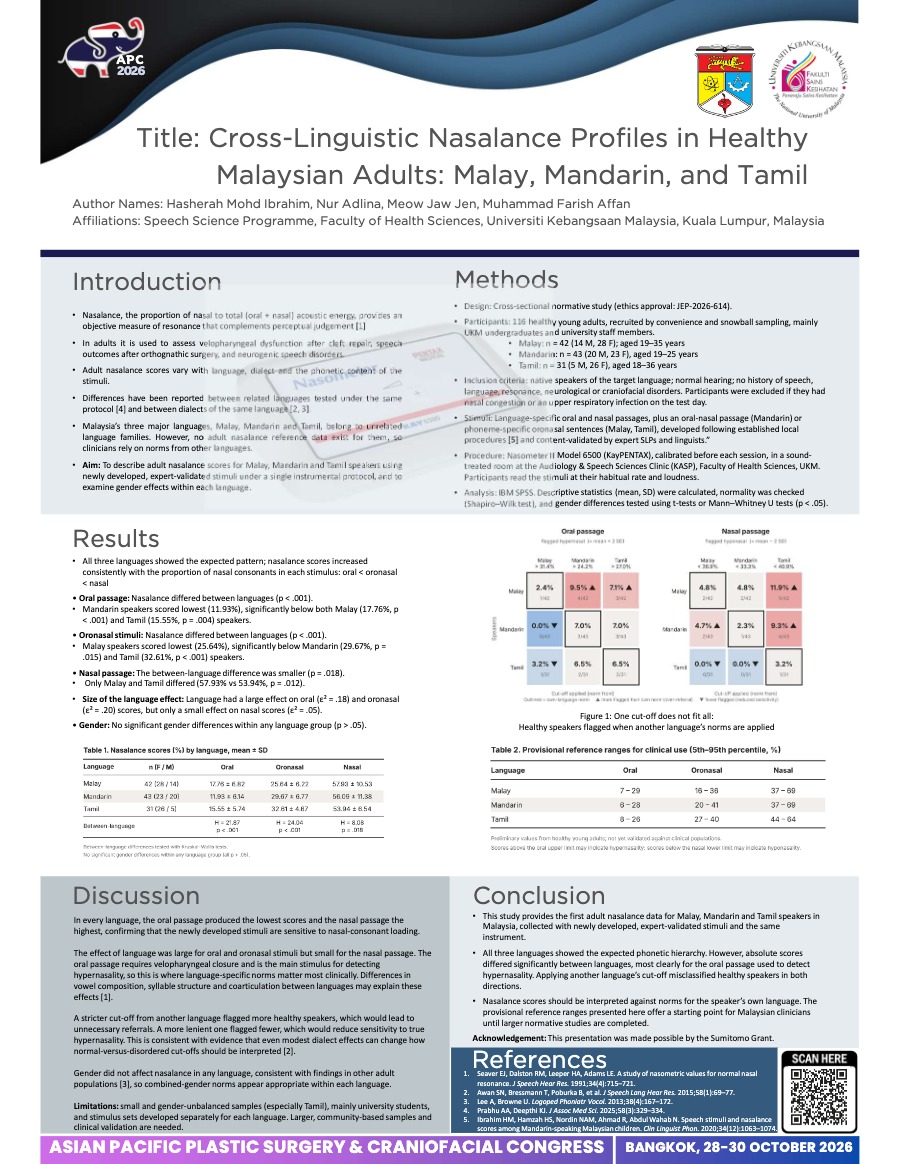
Introduction: Nasalance is an objective acoustic measure of the ratio of nasal to total acoustic energy during speech, used clinically to assess hypernasality and hyponasality. Nasalance values vary across languages and phonetic content, yet Malaysia lacks population-specific norms for Malay-, Mandarin-, and Tamil-speaking adults, and clinicians rely on foreign, pediatric, or mismatched benchmarks. This study compared nasalance profiles across these three major Malaysian language communities using harmonized stimuli and identical instrumentation to determine whether language-specific norms are clinically warranted.
Materials & Methods: A total of 116 healthy adults participated: 42 Malay speakers (14 males, 28 females; aged 19 to 35 years), 43 Mandarin speakers (20 males, 23 females; aged 19 to 25 years), and 31 Tamil speakers (5 males, 26 females; aged 18 to 36 years). Each participant read an oral passage, a nasal passage, and a set of oronasal phoneme-loaded sentences developed and validated in their respective language. Nasalance was recorded using the Nasometer II (KayPENTAX, Model 6500). Kruskal-Wallis tests with Dunn's post-hoc comparisons (Bonferroni-corrected) examined between-language differences for each passage type; Mann-Whitney U and independent samples t-tests examined gender differences within each language.
Results: Significant between-language differences were found for the oral passage (H=21.87, p<0.001), nasal passage (H=8.08, p=0.018), and oronasal sentences (H=24.04, p<0.001). Mandarin speakers produced significantly lower oral passage nasalance than Malay and Tamil speakers (p<0.001, p=0.017). Malay speakers showed significantly higher nasal passage scores than Tamil speakers (p=0.014), and significantly lower oronasal scores than Mandarin (p=0.017) and Tamil (p<0.001) speakers. No gender differences were found within any language group (p>0.05).
Conclusion: Nasalance profiles differ significantly across Malay, Mandarin, and Tamil speakers even when instrumentation, protocol, and stimulus construction are held constant within one country. Language-specific normative data are therefore clinically necessary in Malaysia's multilingual healthcare setting, and norms should not be generalized across language communities.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0027
- Title
- From Cleft to Contour: Post-operative Nasal Molding Using The PSU Nasal Clip in a Patient with Cleft lip and Alveolus
- Author(s)
- PANUMAT INTHAMON
- Affiliation
- Center of Excellence in Correction and Rehabilitation of Dentofacial Deformities Faculty of Dentistry, Prince of Songkla University, Hat Yai, Thailand
From Cleft to Contour: Post-operative Nasal Molding Using The PSU Nasal Clip in a Patient with Cleft lip and Alveolus CP-0027
PANUMAT INTHAMON · Case Study
Introduction
Cleft lip are associated with nasolabial and maxillary dentoalveolar defects. Early dental and surgical treatment aims to restore function and achieve acceptable esthetic outcomes, reducing psychosocial challenges and improving the quality of life for both patients and their parents.
Materials and methods: Case report
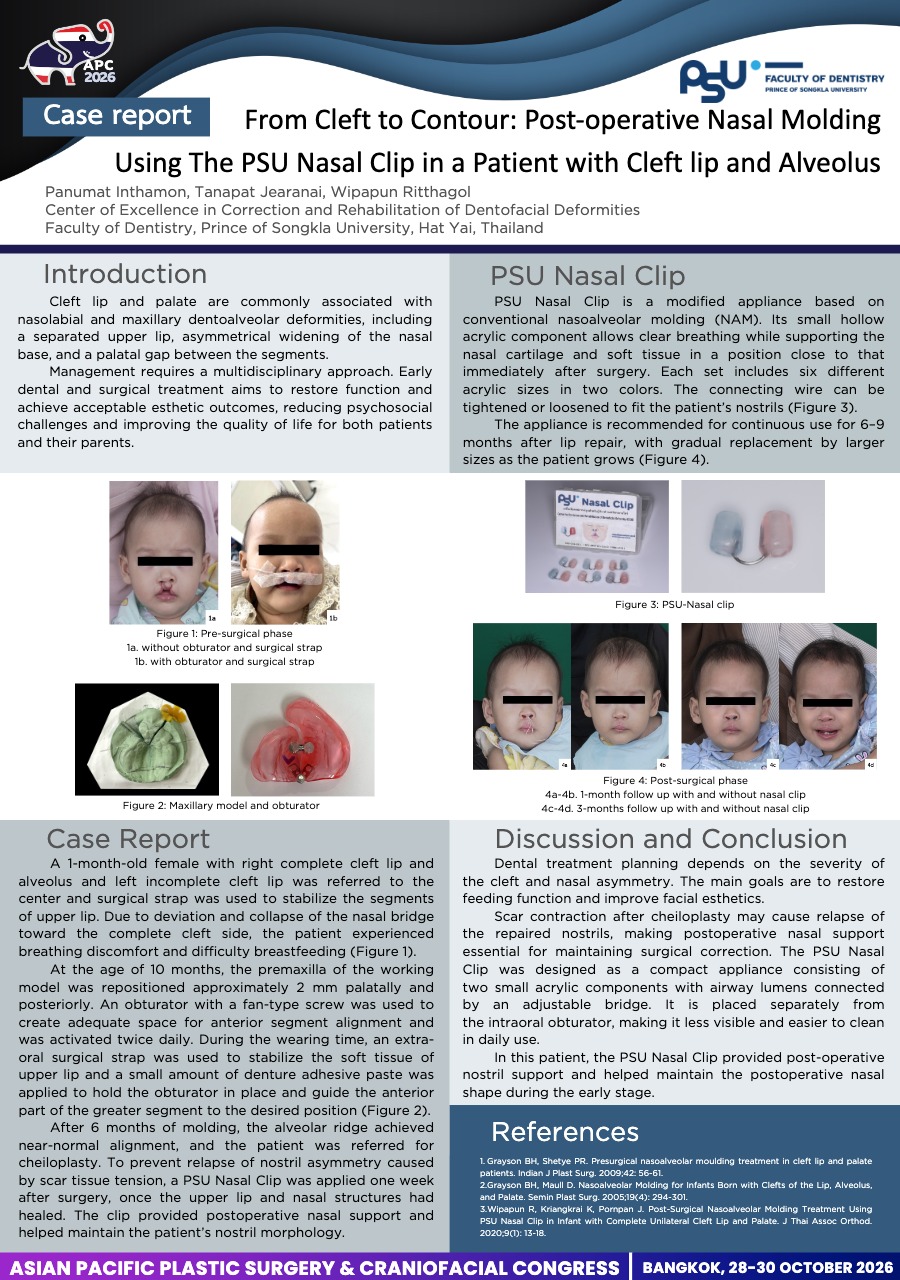
A 1-month-old female with right complete cleft lip and alveolus and left incomplete cleft lip was referred to the center. Due to collapse of the nasal bridge toward the complete cleft side, the patient experienced breathing discomfort and difficulty breastfeeding.
After 6 months of molding, the alveolar ridge achieved near-normal alignment, and the patient was referred for cheiloplasty.
To prevent relapse of nostril, a PSU Nasal Clip was applied one week after surgery, once the upper lip and nasal structures had healed. The clip provided postoperative nasal support and maintain the patient’s nostril morphology. The PSU Nasal Clip has small hollow acrylic component allows clear breathing while supporting the nasal cartilage and soft tissue in a position. Each set includes 6 different acrylic sizes in 2 colors. The connecting wire can be adjusted to fit the nostrils. The appliance is recommended for continuous use for 6–9 months after lip repair, with gradual replacement by larger sizes as the patient grows.
Conclusion
Dental treatment planning depends on the severity of the cleft and nasal asymmetry. The main goals are to restore feeding function and esthetics. Scar contraction after cheiloplasty may cause relapse, making postoperative nasal support essential for maintaining surgical correction.
The PSU Nasal Clip was designed as a compact appliance. It is placed separately from the intraoral obturator, making it less visible and easier to clean in daily use. The PSU Nasal Clip provided post-operative nostril support and maintain the postoperative nasal shape.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
Page 3 of 4 (45 poster(s))
Double-click or press Esc to close · Scroll to zoom