CP-0019
Digital Poster
Filter:
Less rigid fixation with non - absorbable sutures in sagittal craniosynostosis in single instituition experiences (Hospital Tunku Azizah, Kuala Lumpur , Malaysia) CP-0019
Hamidah Mohd Zainal · Case Study

Introduction:
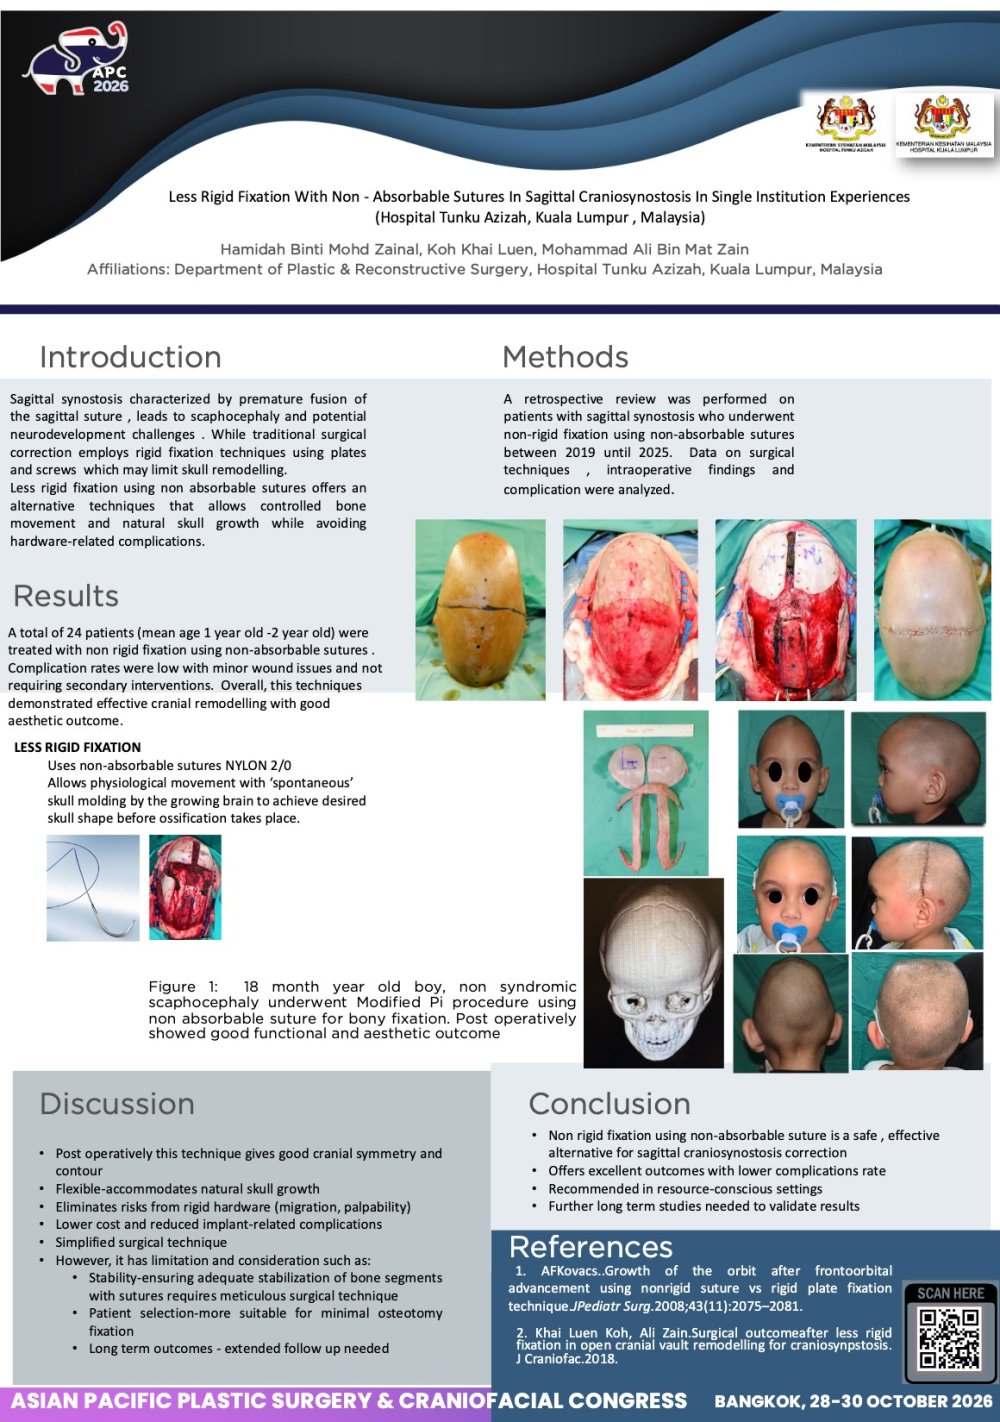
Sagittal Synostosis is the most common craniosynostosis in our center. We performed Cranial vault remodelling using Modified Pi techniques. Due to financial constraints we use non absorbable sutures for bone fixation.
Methods
Retrospective study analysed patient who underwent open anterior cranial vault surgery for saggittal synostosis between . 2017 until 2025 were performed. Demographic data, surgical complication, postoperative asthetic outcomes evaluated. Surgical technique using Modified Pi techniques with bitemporal expansion using non absorbable sutures.
Results:
25 patients of sagittal synostosis with mean age 1.7 month operated using modified pi technique and all cases use nylon 2/0 for bone fixation. Non of our series of case has complication related to suture used, ie: suture extrusion, infection or wound breakdown. All the cases gives good aesthetic outcome.
Conclusion:
Our technique of open cranial vault reconstruction with non absorbabble sutures nylon 2/0 as sole methods of fixation has resulted in good aesthethic outcome with no reoperation and complication rate.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0017
- Title
- Healthcare Access to Cleft Care in Southeast Asia: A Scoping Review of Barriers and Facilitators
- Author(s)
- Chloe Shada Nareswari
- Affiliation
- Universitas Indonesia
Healthcare Access to Cleft Care in Southeast Asia: A Scoping Review of Barriers and Facilitators RP-0017
Chloe Shada Nareswari · Research
Introduction: Cleft lip and palate (CL/P) requires timely, long-term multidisciplinary care to optimize functional and psychosocial outcomes. Southeast Asia faces substantial disparities in healthcare resources and geographic access, yet evidence on cleft care accessibility across the region remains fragmented. This scoping review mapped barriers and facilitators influencing access to cleft care in Southeast Asia.
Methods: This scoping review was conducted in accordance with the Joanna Briggs Institute (JBI) methodology and PRISMA-ScR. A comprehensive search of PubMed, CENTRAL, Scopus, and Wiley Online Library was performed using controlled vocabulary (MeSH where applicable), free-text terms, synonyms, and related terms for CL/P, healthcare access, and Southeast Asian countries. Study selection was conducted in Covidence according to predefined eligibility criteria. Data were charted and synthesized using thematic analysis.
Results: Sixty-four studies were included. Five categories of barriers were identified: financial (travel costs, low socioeconomic status), geographic (long travel distance), health system (challenging referral procedures, prolonged surgical waiting times, inadequate facilities, absence of a follow-up reminder system), workforce (limited trained medical personnel), and information, communication, and health literacy (limited knowledge of available cleft services, language barriers, low health literacy, limited communication skills). Facilitators were grouped into five domains: health information and patient education (social media, guidebooks, translated CLEFT-Q/assessment tools, specialist and peer advice), care coordination and service delivery innovations (telemedicine, community-based speech therapy, speech camps, treatment scheduling method, integrated care and referral systems), workplace capacity building (training programs), health system strengthening (registries, geographic information systems, information and communication technology, healthcare networks), and community and organizational support (NGOs, volunteer mission teams, healthcare insurance).
Conclusion: Access to cleft care in Southeast Asia remains limited by multiple barriers. Improving outcomes requires context-specific strategies, stronger health systems, and regional collaboration. Future research should address psychosocial factors, cultural beliefs, and patient and family perspectives.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0015
- Title
- LOWER-LID SWITCH FLAP TO MAINTAIN FUNCTION AND AESTHETIC RESULTS OF UPPER EYELID AFTER FULL-THICKNESS WIDE EXCISION OF SQUAMOUS CELL CARCINOMA
- Author(s)
- Faustine Emanuela
- Affiliation
- Plastic Reconstructive and Aesthetic Surgery Unit, Pusat Angkatan Laut dr. Ramelan Hospital, Surabaya, Indonesia
LOWER-LID SWITCH FLAP TO MAINTAIN FUNCTION AND AESTHETIC RESULTS OF UPPER EYELID AFTER FULL-THICKNESS WIDE EXCISION OF SQUAMOUS CELL CARCINOMA CP-0015
Faustine Emanuela · Case Study
Background: Eyelid tumors are relatively rare and heterogeneous. Malignant eyelid tumors tend to display aggressive histopathological behavior, complete surgical excision is essential in their management. Achieving maximal preservation of both cosmetic appearance and function remains a challenging task even for experienced surgeons.
Objective: To describe a two-stage lower-lid switch flap technique for reconstructing the upper eyelid and perserving its function after full-thickness wide excision of squamous cell carcinoma.
Methods: A case report of a 45-year-old man with squamous cell carcinoma of the right upper eyelid.
Result: Reconstruction after full-thickness excision involving more than 75% of the upper eyelid must not only close the defect but also preserve eyelid function. The porcedure was performed in two stages: the lower-eyelid flap was first attached to the upper-eyelid defect, and the flap was the devided after 21 days. Ini ths case, the defect was closed using a lower-lid switch flap based on the marginal arcade, a technique chosen to preserve the tarsal plate and levator palpebrae muscle so that eyelid openinig and closing remained functional. This approach yielded good functional and aesthetic outcomes without complications.
Conclusion: Malignant neoplasms are a leading indication for reconstructive surgery in the periorbital region. Closing an upper-eyelid defect without reconstructing the levator palpebrae muscle is restored and the tarsus is preserved as the lid margin, thereby maintaining eyelid function.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0031
- Title
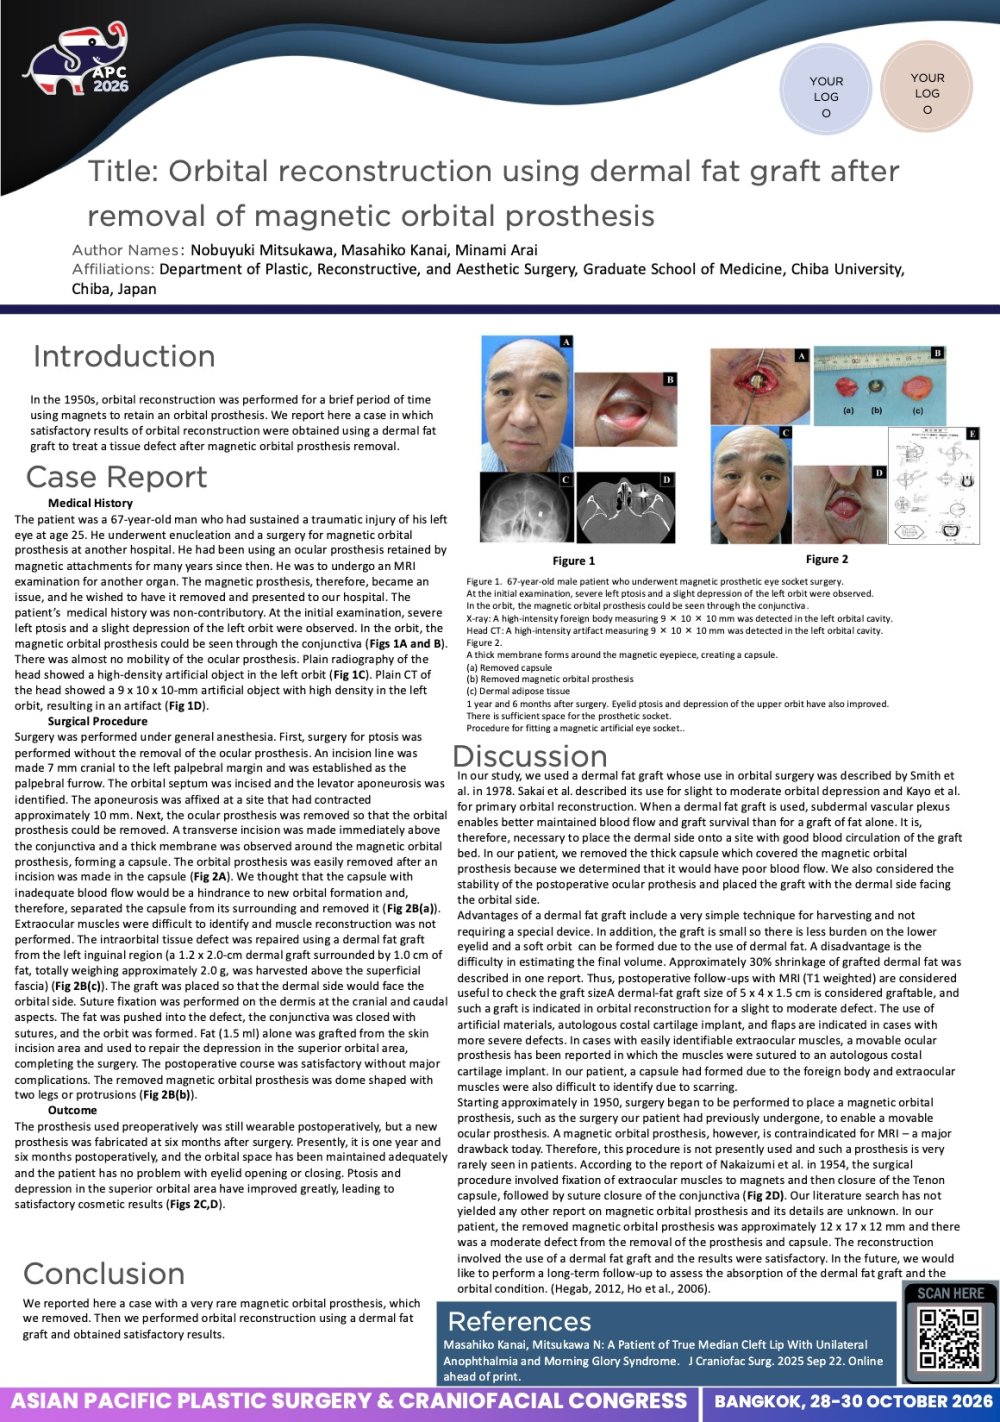
- Orbital Reconstruction Using Dermal Fat Graft After Removal of Magnetic Orbital Prosthesis
- Author(s)
- Nobuyuki Mitsukawa
- Affiliation
- Department of Plastic, Reconstructive, and Aesthetic Surgery, Graduate School of Medicine, Chiba University
Orbital Reconstruction Using Dermal Fat Graft After Removal of Magnetic Orbital Prosthesis CP-0031
Nobuyuki Mitsukawa · Case Study
Introduction: We present a case of dermal fat graft for eye socket reconstruction after the removal of magnetic orbital prosthesis.
Case Report :A 68-year-old male who had a damage to the left eye by trauma more than 40 years ago, and the eyeball was removed and magnetic orbital prosthesis surgery was performed. The patient was using the magnetic orbital prosthesis for many years, but upon receiving MRI examination, the magnet became an obstacle, and came to our department to remove it. At the first visit, pelvic drops on the affected side and mild depression of the upper eyelid were observed, and the magnetic orbital prosthesis was transparent through the conjunctiva. Under general anesthesia, made incision horizontally to the conjunctiva and removed magnetic orbital prosthesis. After removing the magnetic orbital prosthesis, the dermal fat collected from the groin was transplanted excessively to the tissue defect, and the wound was closed. And also the fat injection was performed to the upper eyelid.
Results/Conclusion: 2 years after the operation, condition of the dermal fat graft is stable, there is no problem wearing the new orbital prosthesis.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0032
- Title
- An Anatomic Investigation of Human Fetal Upper Eyelid
- Author(s)
- Nobuyuki Mitsukawa
- Affiliation
- Department of Plastic and Reconstructive Surgery, Chiba University Graduate School of Medicine
An Anatomic Investigation of Human Fetal Upper Eyelid RP-0032
Nobuyuki Mitsukawa · Research
Introduction: In this study, the authors investigated the anatomic morphology of the upper eyelid in prenatal human fetuses to elucidate the cause of congenital palpebral conditions such as congenital blepharoptosis. Although much has been published on the anatomy of the adult upper eyelid, hardly any reports have dealt with neonatal morphology in the immediate postpartum period or infants and children. From a developmental perspective, to better understand the development and aging effects in the upper eyelid, knowledge is needed of the anatomic characteristics of the upper eyelid in neonates immediately after birth. Also, to elucidate the cause of congenital blepharoptosis, the authors investigated the anatomy of the upper eyelid in human fetuses.
Materials & Methods: Subjects comprised 6 Japanese fetuses between 6 and 10 months of gestation for a total of 12 eyelids. Sagittal tissue slices of the excised upper eyelid were embedded in paraffin, sliced thinly, then stained with HE and Van Gieson. The specimens were carefully examined under light microscopy. Next, these samples were compared with adult upper eyelid tissue images to determine differences in development and morphology.
Results: Fetal characteristics observed were as follows: the morphologic characteristics of the palpebrae superioris muscle and levator aponeurosis were underdeveloped and connections to the orbicularis oculi muscle were sparse, whereas the Müller muscle was markedly thicker than those in adults.
Conclusion: Fetal eyes tend to be closed in amniotic fluid, and so before fetuses begin to move, the levator palpebrae superioris muscle tends to be poorly developed, whereas eye-opening is speculated to be controlled primarily by Müller muscle. Findings suggest muscle fibers develop due to eye-opening movements, and the differentiation and development of the levator palpebrae superioris muscle are believed to be closely related to the development of congenital blepharoptosis.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0033
- Title
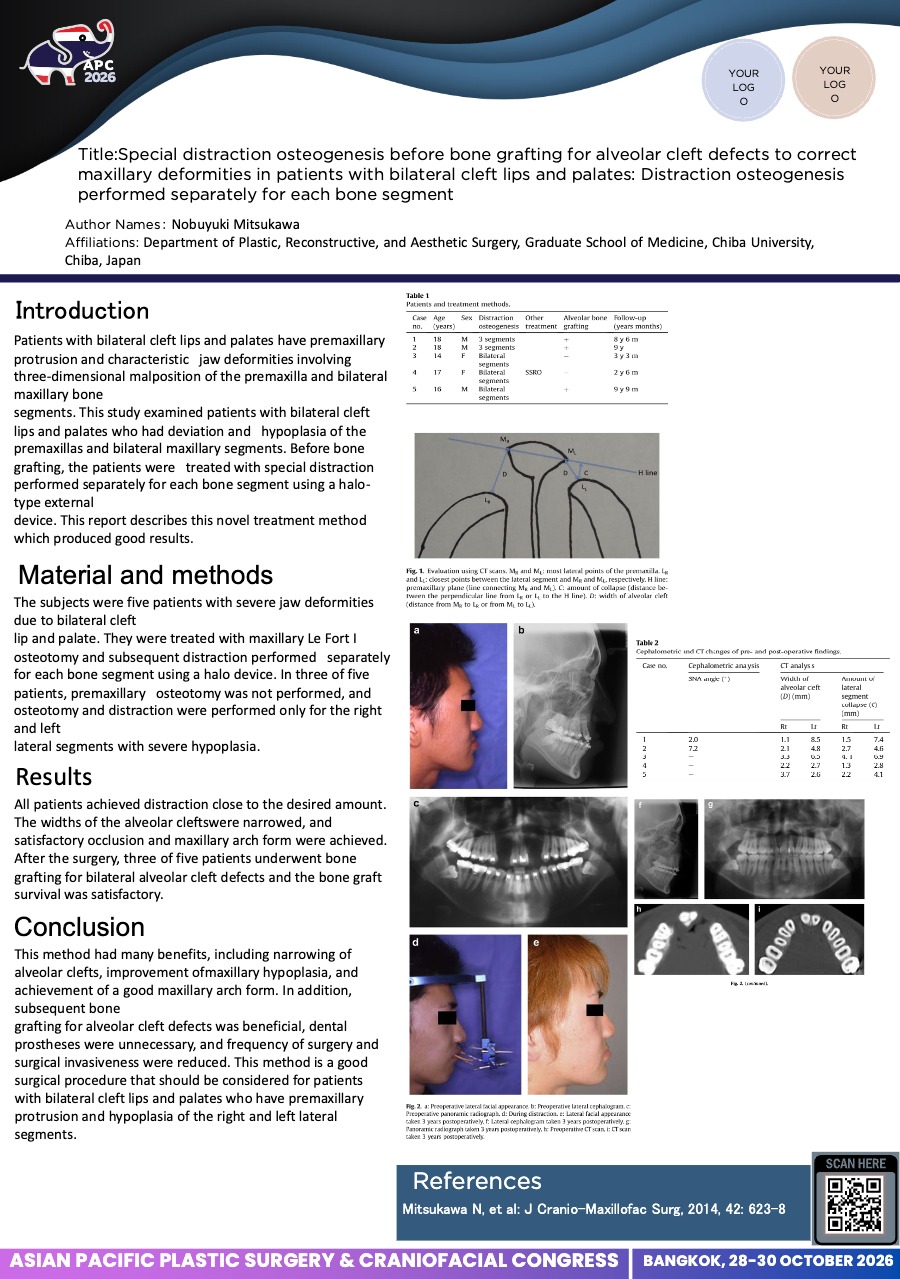
- Special distraction osteogenesis before bone grafting for alveolar cleft defects to correct maxillary deformities in patients with bilateral cleft lips and palates
- Author(s)
- Nobuyuki Mitsukawa
- Affiliation
- Department of Plastic, Reconstructive, and Aesthetic Surgery, Graduate School of Medicine, Chiba University
Special distraction osteogenesis before bone grafting for alveolar cleft defects to correct maxillary deformities in patients with bilateral cleft lips and palates RP-0033
Nobuyuki Mitsukawa · Research
Introduction: Patients with bilateral cleft lips and palates have premaxillary protrusion and characteristic jaw deformities involving three-dimensional malposition of the premaxilla and bilateral maxillary bone segments. This study examined patients with bilateral cleft lips and palates who had deviation and hypoplasia of the premaxillas and bilateral maxillary segments. Before bone grafting, the patients were treated with special distraction performed separately for each bone segment using a halo-type external device. This report describes this novel treatment method which produced good results.
Material and methods: The subjects were five patients with severe jaw deformities due to bilateral cleft lip and palate. They were treated with maxillary Le Fort I osteotomy and subsequent distraction performed separately for each bone segment using a halo device. In three of five patients, premaxillary osteotomy was not performed, and osteotomy and distraction were performed only for the right and left lateral segments with severe hypoplasia.
Results: All patients achieved distraction close to the desired amount. The widths of the alveolar clefts were narrowed, and satisfactory occlusion and maxillary arch form were achieved. After the surgery, three of five patients underwent bone grafting for bilateral alveolar cleft defects and the bone graft survival was satisfactory.
Conclusions: This method had many benefits, including narrowing of alveolar clefts, improvement of maxillary hypoplasia, and achievement of a good maxillary arch form. In addition, subsequent bone grafting for alveolar cleft defects was beneficial, dental prostheses were unnecessary, and frequency of surgery and surgical invasiveness were reduced. This method is a good surgical procedure that should be considered for patients with bilateral cleft lips and palates who have premaxillary protrusion and hypoplasia of the right and left lateral segments.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0018
- Title
- The Role of Postoperative Nasal Retainer in Achieving Nasal Symmetry after Modified Subunit Cheilonasorraphy: A Case Series
- Author(s)
- Faustine Emanuela
- Affiliation
- Pusat Angkatan Laut dr. Ramelan Hospital, Surabaya, Indonesia
The Role of Postoperative Nasal Retainer in Achieving Nasal Symmetry after Modified Subunit Cheilonasorraphy: A Case Series CP-0018
Faustine Emanuela · Case Study
Background: Postoperative nasal relapse — loss of alar symmetry and descent of the nasal tip — remains a common problem after primary repair of the cleft lip and nose, in both unilateral and bilateral forms. Postoperative nasal retainers and subunit-based lip closure have each been proposed to address this, but they are rarely reported together, and rarely across both cleft types in the same series.
Objective: To evaluate nasal symmetry and philtrum outcomes achieved by combining a modified subunit cheilonasorraphy — a combined lip-and-nose closure individually adapted to each patient's anatomy — with a postoperative nasal retainer, in patients with unilateral and bilateral cleft lip and nose.
Methods: This is a case series of 6 patients with unilateral an bilateral cleft lip who underwent primary cheilonasorraphy using a modified subunit technique. All patients received a postoperative nasal retainer for 30 days. Outcomes were assessed using clinical image and physician’s clinical evaluation over a follow-up period of January to May 2026.
Result: All six patients showed a rounded, symmetic alar shape without nasal-tip flattening, and the lip philtrum remained well defined postoperatively. No infection, no dehiscence , minimum septum deviation and hypertrophic scar occurred were observed.
Conclusion: Combining a modified-subunit cheilonasorraphy technique with postoperative nasal retainer appears promising for perserving nasal shape and philtrum contour in primary repair to unilateral and bilateral cleft lip. Controlled comparative studies with larger samples and objective measurements are needed to confirm the advantage of this technique over conventional approaches.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RO-0066
- Title
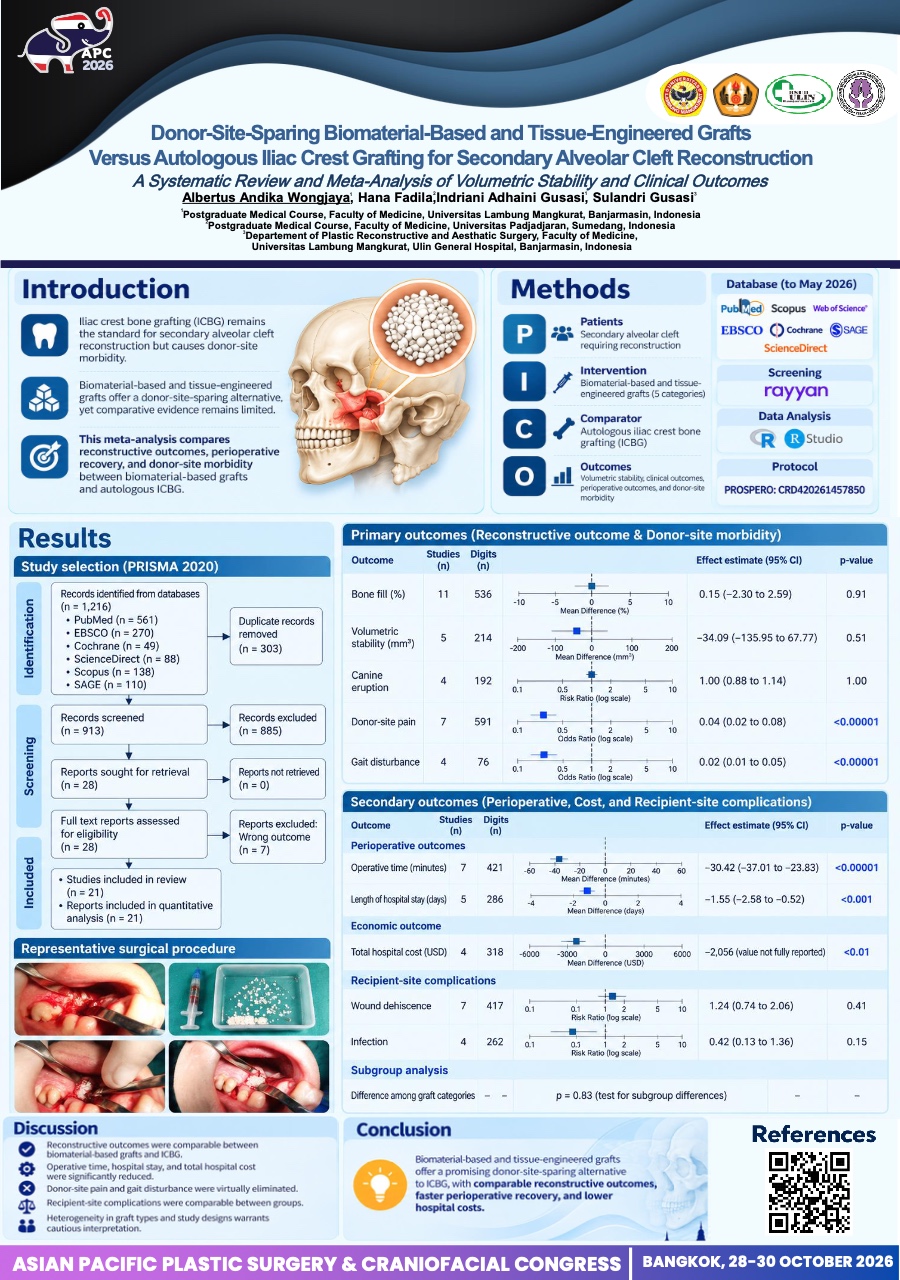
- Donor-Site-Sparing Biomaterial-Based and Tissue-Engineered Grafts versus Iliac Crest Grafting for Secondary Alveolar Cleft Reconstruction: A Systematic Review and Meta-Analysis of Volumetric Stability and Clinical Outcomes
- Author(s)
- Albertus Andika Wongjaya
- Affiliation
- Department of Plastic Reconstructive and Aesthetic Surgery, Faculty of Medicine, Universitas Lambung Mangkurat, Ulin General Hospital, Banjarmasin, Indonesia
Donor-Site-Sparing Biomaterial-Based and Tissue-Engineered Grafts versus Iliac Crest Grafting for Secondary Alveolar Cleft Reconstruction: A Systematic Review and Meta-Analysis of Volumetric Stability and Clinical Outcomes RO-0066
Albertus Andika Wongjaya · Research
Introduction: Despite decades as the reference standard for secondary alveolar cleft reconstruction, iliac crest bone grafting (ICBG) necessitates a second surgical site with well-documented sequelae. Biomaterial-based and tissue-engineered alternatives have emerged, yet no meta-analysis has synthesized their reconstructive, perioperative, economic, and donor-site morbidity outcomes against ICBG.
Methods: Following PRISMA 2020 (PROSPERO: CRD420261457850), six databases (PubMed, Scopus, EBSCO, ScienceDirect, Cochrane, and Sage) were searched through May 2026. Twenty-one studies (N=774; 348 biomaterial, 426 ICBG) spanning five graft categories were analyzed using DerSimonian–Laird random-effects models; zero-event outcomes were pooled via Peto odds ratio. Risk of bias was assessed with RoB-2 and ROBINS-I; certainty with GRADE framework.
Results: Biomaterial-based and tissue-engineered grafts demonstrated comparable bone fill (k=11; MD +0.15%, 95% CI −2.30 to +2.59; P=0.91; I²=0%), volumetric stability (k=5; MD −34.09 mm³, 95% CI −135.95 to +67.77; P=0.51; I²=0%), and canine eruption (k=4; RR 1.00, 95% CI 0.88–1.14; I²=0%), with no difference among graft categories (P=0.83). Operative time was significantly shorter (k=7; MD −30.42 min, 95% CI −37.01 to −23.83; P<0.00001), as was hospital stay (k=5; MD −1.55 days, 95% CI −2.58 to −0.52; P<0.001). Total hospital cost favored biomaterials despite higher material costs (MD −$2,056; P<0.01). Donor-site pain was virtually absent (0/302 vs 59/289; Peto OR 0.04, 95% CI 0.02–0.08; P<0.00001), as was gait disturbance (0/38 vs 38/38; Peto OR 0.02, 95% CI 0.01–0.05; P<0.00001). Recipient-site complications were equivalent: dehiscence (k=7; RR 1.24, 95% CI 0.74–2.06; P=0.41) and infection (k=4; RR 0.42, 95% CI 0.13–1.36; P=0.15).
Conclusion: Biomaterial-based and tissue-engineered grafts achieve reconstructive parity with autologous ICBG while eliminating donor-site morbidity, shortening perioperative recovery, and reducing hospital expenditure, establishing them as a compelling evidence-based alternative for secondary alveolar cleft reconstruction.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0017
- Title
- When the Eyelids Heal Toghether: Two-Lamellar Reconstruction of a Rare Post-Traumatic Medial Canthal Ankyloblepharon
- Author(s)
- Faustine Emanuela
- Affiliation
- Pusat Angkatan Laut Dr. Ramelan Hospital, Surabaya, Indonesia
When the Eyelids Heal Toghether: Two-Lamellar Reconstruction of a Rare Post-Traumatic Medial Canthal Ankyloblepharon CP-0017
Faustine Emanuela · Case Study
Purpose: Post-traumatic medial canthal ankyloblepharon is an uncommon acquired cicatricial eyelid deformity that can result in severe eyelid contracture, visual obstruction, and functional impairment. When both anterior and posterior lamellar tissues are inivolved, simple adhesiolysis may be insufficient and may predispose to recurrent contracture. We present a two -lamellar reconstrucitve strategy combining complete synechial release, sequential Z-plasty, and vascularized iniferior palpebral conjungtival tissue.
Methods: A 66-year-old man presented with a unilateral left medial canthal eyelid deformity approximately one year following a motor vehicle accident. The upper and lower eyelids were cicatrically fused from the medial canthus toward the central one-third orf the eyelid, resulting in restricted eyelid opening and visual impairment. Intraoperative exploration demonstrated dense cicatricial synechiae with contracture involving both the superior and inferior eyelids and disruption of the anterior and posterior lamellar architecture. Complete synechial release was performed. Multiple z-plasties were designed on the superior/anterior lamella to reorient the scar and provide tissue lengthening. Inferior eyelid contracture was release through a lower blepharoplasty-type approach. The resulting posterior lamellar defect was reconstructed using an inferior palpebral conjunctival wedge flap. Providing vascularized native tissue coverage.
Result: The procedure restored separation of the upper and lower eyelids re-established the medial canthal architecture. Postoperatively, the patient achieved eyelid opening comparable to the contralateral eye with satisfactory eyelid closure. No wound infection or dehiscence occurred. The patient reported satisfactory functional and aesthetic improvement with a marked improvement in quality of life.
Conclusion: Post-traumatic medial canthal ankyloblepharon should be considered a complex three-dimensional cicatricial deformity rather than a simple eyelid adhesion. Successful reconstruction requires simultaneous correction of the contractile forces and restoration of the ephitelialized surfaces of both eyelid lamellae. The combiniation of synechial release, Z-plasty-based anterior lamellar lengthening, and vascularized conjunctival resurfacing provides a tissue-perservinig release-reorient-resurface stratefy for restoring eyelid separation and function.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0022
- Title
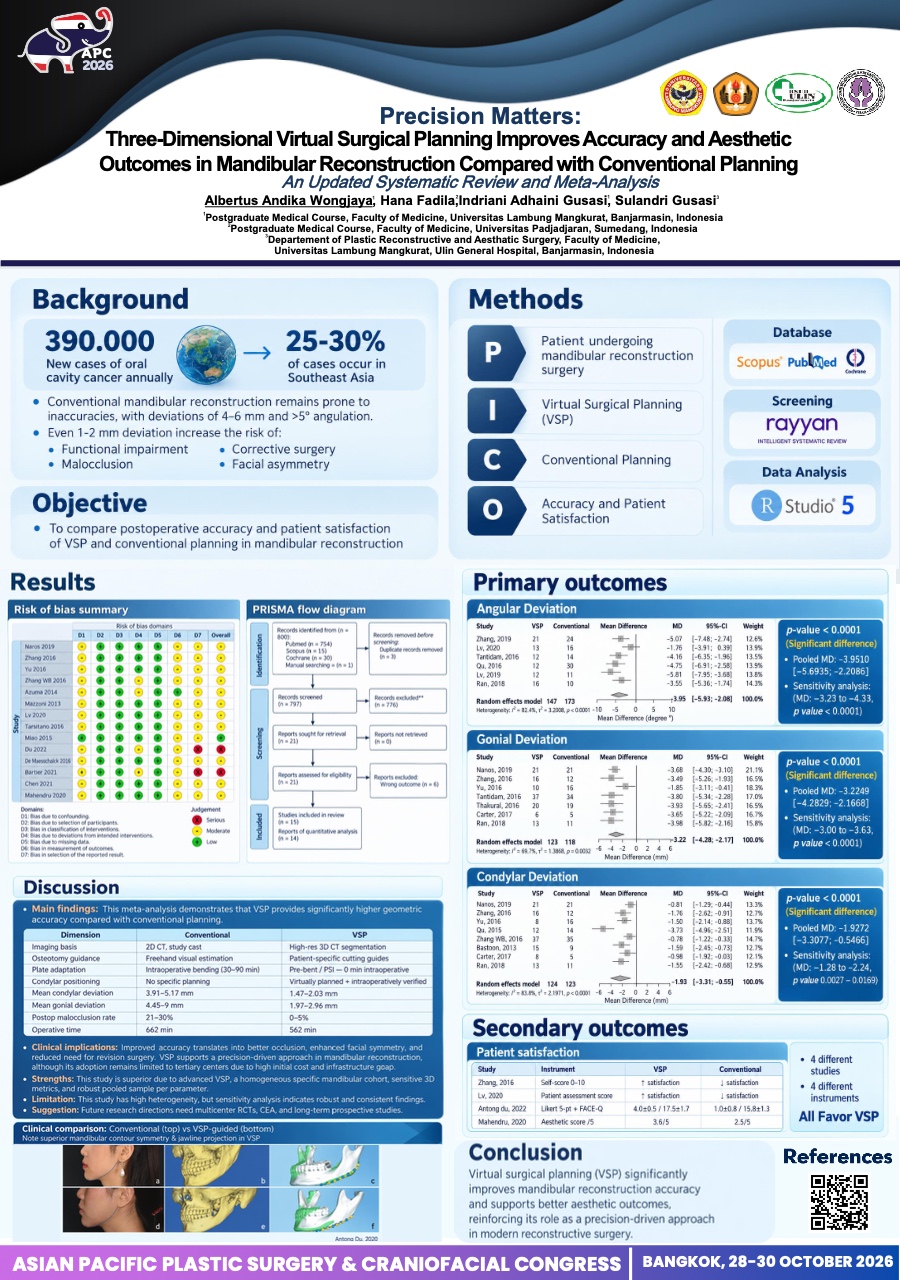
- TOWARD PRECISION IN MANDIBULAR RECONSTRUCTION: AN UPDATED SYSTEMATIC REVIEW AND META-ANALYSIS OF THREE-DIMENSIONAL VIRTUAL SURGICAL PLANNING VERSUS CONVENTIONAL PLANNING
- Author(s)
- Albertus Andika Wongjaya
- Affiliation
- Departement of Plastic Reconstructive and Aesthatic Surgery, Faculty of Medicine, Universitas Lambung Mangkurat, Ulin General Hospital, Banjarmasin, Indonesia
TOWARD PRECISION IN MANDIBULAR RECONSTRUCTION: AN UPDATED SYSTEMATIC REVIEW AND META-ANALYSIS OF THREE-DIMENSIONAL VIRTUAL SURGICAL PLANNING VERSUS CONVENTIONAL PLANNING RP-0022
Albertus Andika Wongjaya · Research
Introduction:
Mandibular reconstruction remains a major challenge in craniofacial surgery because precise
restoration of mandibular anatomy is essential for both functional recovery and facial
symmetry. Conventional planning relies on two-dimensional imaging and intraoperative
freehand techniques, which may limit accurate reproduction of complex three-dimensional
anatomy. However, robust evidence demonstrating whether three-dimensional virtual surgical
planning (VSP) improves reconstruction accuracy and patient-perceived aesthetic outcomes
remains limited. Therefore, this study evaluated the effectiveness of VSP compared with
conventional planning in mandibular reconstruction.
Methods:
A systematic review and meta-analysis were conducted following the PRISMA guidelines.
Searches were performed in PubMed, Scopus, and Cochrane to identify studies comparing
VSP-assisted mandibular reconstruction with conventional surgical planning. Quantitative
outcomes related to postoperative accuracy and facial symmetry, including angular deviation,
gonial positional deviation, and condylar positional deviation, were analyzed in R software
(metafor package). Patient-reported aesthetic outcomes were summarized qualitatively.
Results:
A total of 15 studies were included in the final analysis. The outcomes were grouped into two
categories: quantitative reconstruction accuracy and patient-reported aesthetic outcomes. The
pooled analysis demonstrated significantly lower postoperative angular deviation in the VSP
group (MD −3.95°, 95% CI −5.69 to −2.21; I² = 82.4%). Similarly, VSP significantly reduced
gonial positional deviation (MD −3.22 mm, 95% CI −4.28 to −2.17, I2 = 68.7%) and condylar
positional deviation (MD −1.93 mm, 95% CI −3.31 to −0.55, I2 = 82.8%). Studies evaluating
patient-reported outcomes consistently demonstrated higher aesthetic satisfaction among
patients undergoing VSP-assisted reconstruction.
Conclusion:
Three-dimensional virtual surgical planning significantly improves the accuracy of mandibular
reconstruction and is associated with higher patient-reported aesthetic satisfaction. These
findings support the integration of three-dimensional virtual surgical planning technologies to
achieve more precise, predictable, and patient-centered outcomes in craniofacial reconstructive
surgery.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0032
- Title
- Combination of Various Maxillary Distraction Osteogenesis for Patients with Severe Complicated Cleft Maxillary Hypoplasia
- Author(s)
- Nobuyuki Mitsukawa
- Affiliation
- Department of Plastic, Reconstructive, and Aesthetic Surgery, Graduate School of Medicine, Chiba University
Combination of Various Maxillary Distraction Osteogenesis for Patients with Severe Complicated Cleft Maxillary Hypoplasia CP-0032
Nobuyuki Mitsukawa · Case Study
Cleft maxillary hypoplasia (CMH) is a common sequela in patients with cleft lip and palate (CLP) who have undergone surgical and orthodontic interventions. Le Fort I maxillary distraction osteogenesis (DO) using a halo-type external distraction device is a well-established technique for maxillary advancement. However, simple anterior advancement may not yield satisfactory outcomes in cases involving severe segmental deviations. We reported our success in utilizing a combination of various maxillary DO and bone transport techniques to correct severe, complicated CMH.
Methods: The patient was a 13-year-old girl with Angle Class III malocclusion and a history of congenital left CLP. She had undergone prior corrective surgeries, including cheiloplasty at 3 months of age, palatoplasty at 14 months, and rhinoplasty at 5 years.
Results/Conclusion: Our approach achieved favorable functional and aesthetic outcomes by addressing the complex deformities between maxillary segments. This case highlights the effectiveness of various DO strategies in managing severe, complicated CMH.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0025
- Title
- Alveolar Bone Grafting in Patients with Cleft Lip and Palate: An 11 years Retrospective Review from Sarawak General Hospital
- Author(s)
- Fathin alyaa Mohamad farid
- Affiliation
- Sarawak General Hospital, Malaysia
Alveolar Bone Grafting in Patients with Cleft Lip and Palate: An 11 years Retrospective Review from Sarawak General Hospital RP-0025
Fathin alyaa Mohamad farid · Research
Background:
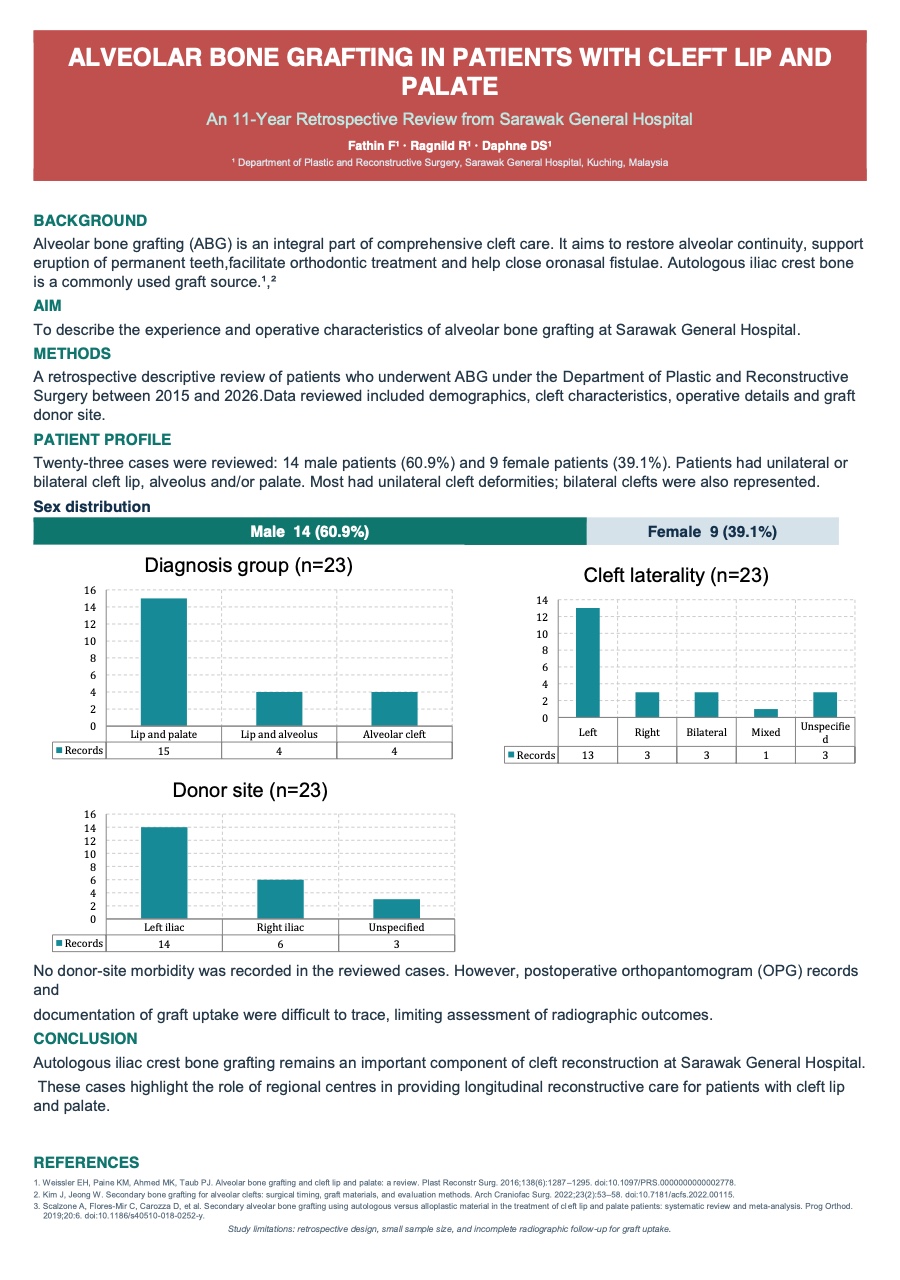
Alveolar bone grafting is an essential component of comprehensive cleft care. It aims to restore alveolar continuity, provide bony support for eruption of the permanent dentition, facilitate orthodontic treatment, and closure of oronasal fistulae. Autologous iliac crest bone remains a commonly used graft source. We describe our experience with alveolar bone grafting at Sarawak General Hospital.
Methods:
A retrospective descriptive review was conducted of patients who underwent alveolar bone grafting under the Plastic and Reconstructive Surgery Department between 2015 and 2026(11years). Data on patient demographics, cleft characteristics, operative details, graft donor site.
Results:
A total of 23 reviewed cases included 9 female patients and 14 male patients with age ranging from 11 years old to 2 years old with unilateral and bilateral cleft lip, alveolus and/or palate. Most patients had unilateral cleft deformities, while bilateral clefts were also represented. Patients underwent alveolar bone grafting using autologous bone harvested predominantly from the anterior iliac crest. Both left and right iliac crest donor sites were utilised according to operative requirements.
Several patients underwent concomitant procedures, including lip revision, correction of nostril, and dermal fat grafting. Operative procedures were performed electively under general anaesthesia. Recorded operative durations varied from approximately 71 to 169 minutes. The cases demonstrated no donor site morbidity. however, our limitation was in tracing the OPG / bone graft uptake.
Conclusion:
Alveolar bone grafting using autologous iliac crest bone remains an important component of cleft reconstruction at our centre. This study reflects the role of regional centres in providing longitudinal reconstructive care for patients with cleft lip and palate.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
Page 1 of 4 (45 poster(s))
Double-click or press Esc to close · Scroll to zoom