CP-0020
Digital Poster
Filter:
Craniosynostosis in East Malaysia: Diagnostic and Surgical Challenges in a Case Series from Regional Tertiary Centre CP-0020
Fathin alyaa Mohamad farid · Case Study
Background:
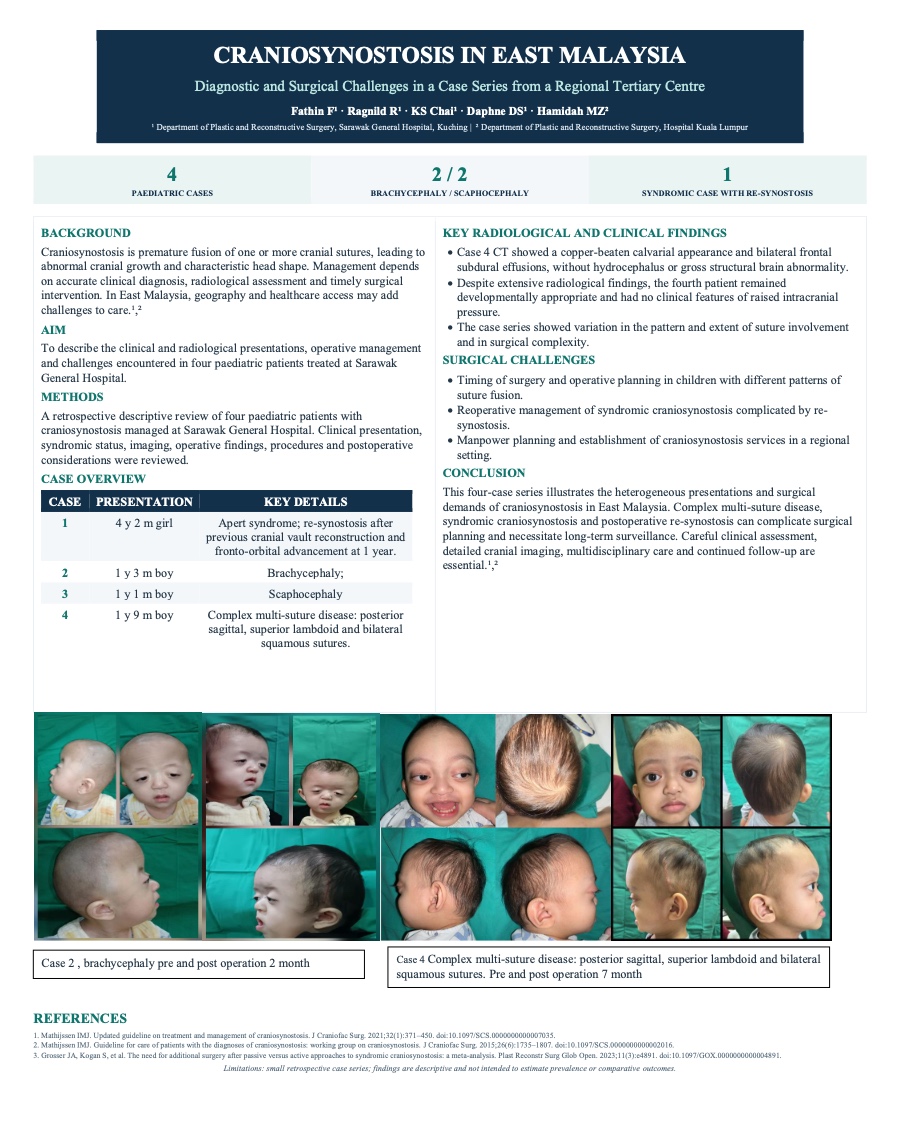
Craniosynostosis is characterised by premature fusion of one or more cranial sutures, resulting in abnormal cranial growth and characteristic skull deformities. Management requires accurate identification of affected sutures, appropriate radiological assessment, and timely surgical intervention. In East Malaysia, geographical and healthcare access considerations may present additional challenges in the diagnosis and management of these uncommon conditions. We describe our experience managing paediatric craniosynostosis at Sarawak General Hospital, highlighting the varied clinical and radiological presentations and surgical challenges encountered.
Methods:
A retrospective descriptive review was conducted of four paediatric patients with craniosynostosis managed at Sarawak General Hospital. Clinical presentation, syndromic status, radiological findings, operative findings, surgical procedures, and postoperative considerations were reviewed.
Four patients were identified, comprising two with brachycephaly and two with scaphocephaly. The cases demonstrated considerable heterogeneity in suture involvement and surgical complexity. A 4-year-2-month-old girl with Apert syndrome developed re-synostosis following previous cranial vault reconstruction and fronto-orbital advancement at one year of age. Reoperation demonstrated fusion of bilateral coronal, sagittal and lambdoid sutures and the anterior fontanelle. Redo cranial vault remodelling using a modified Pi technique with fronto-orbital re-advancement was performed.
A 1-year-3-month-old boy with brachycephaly underwent cranial vault remodelling using a modified Pi technique. A 1-year-1-month-old boy with scaphocephaly and isolated sagittal synostosis underwent cranial vault remodelling. The fourth patient, aged 1 year 9 months, had complex craniosynostosis involving the posterior sagittal, superior lambdoid and bilateral squamous sutures. CT demonstrated a copper-beaten calvarium with bilateral frontal subdural effusions without hydrocephalus. Despite extensive radiological abnormalities, he remained developmentally appropriate without clinical features of raised intracranial pressure.
This case series highlights the challenges of managing craniosynostosis, particularly complex multi-suture disease, syndromic craniosynostosis, and postoperative re-synostosis. Careful clinical assessment, detailed cranial imaging, multidisciplinary care, appropriate surgical timing, and long-term surveillance are essential for optimal management in the regional setting.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0015
- Title
- Orthodontic Management Protocols in Orthognathic Surgery for Cleft and Non-Cleft and Their Treatment Outcomes: A Systematic Review
- Author(s)
- WAN SALBIAH WAN ABDUL RAZAK
- Affiliation
- University Technology MARA / Oral Health Division , The Ministry of Health, Malaysia
Orthodontic Management Protocols in Orthognathic Surgery for Cleft and Non-Cleft and Their Treatment Outcomes: A Systematic Review RP-0015
WAN SALBIAH WAN ABDUL RAZAK · Research

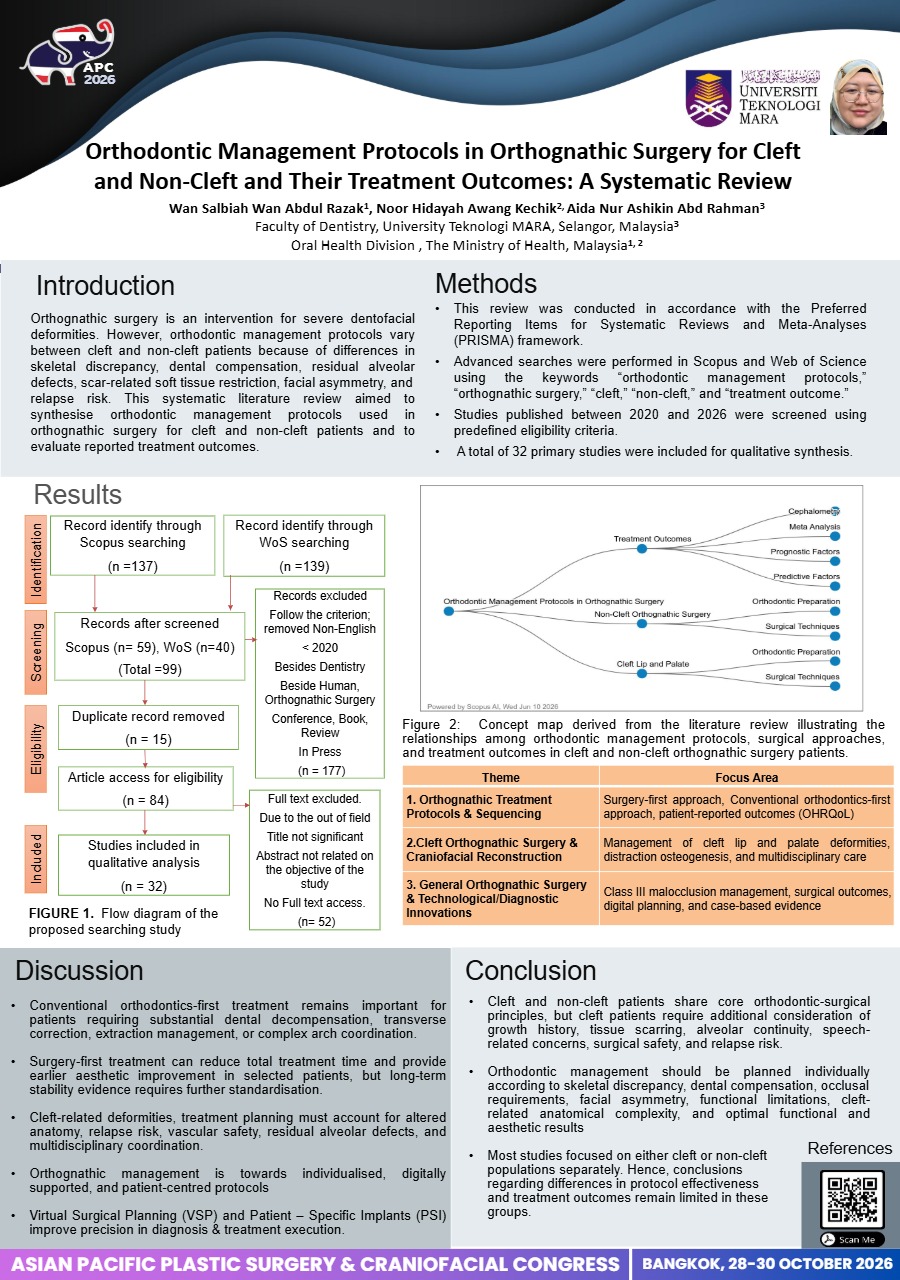
Background: Orthognathic surgery is an established intervention for severe dentofacial deformities; however, orthodontic management protocols vary between cleft and non-cleft patients because of differences in skeletal discrepancy, dental compensation, residual alveolar defects, scar-related soft tissue restriction, facial asymmetry, and relapse risk. This systematic literature review aimed to synthesise orthodontic management protocols used in orthognathic surgery for cleft and non-cleft patients and to evaluate reported treatment outcomes.
Methods: This review was conducted in accordance with the Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) framework. Advanced searches were performed in Scopus and Web of Science using the keywords “orthodontic management protocols,” “orthognathic surgery,” “cleft,” “non-cleft,” and “treatment outcome.” Studies published between 2020 and 2026 were screened using predefined eligibility criteria. A total of 32 primary studies were included for qualitative synthesis.
Results: Three major themes were identified: orthognathic treatment protocols and sequencing; cleft orthognathic surgery and craniofacial reconstruction; and general orthognathic surgery with technological and diagnostic innovations. Conventional orthodontics-first protocols remained important for dental decompensation, arch coordination, extraction management, and correction of complex transverse, vertical, and asymmetrical discrepancies. Surgery-first protocols demonstrated reduced overall treatment duration, earlier facial improvement, and acceptable skeletal stability in selected skeletal Class III cases. In cleft-related deformities, treatment commonly required staged orthodontic preparation, multidisciplinary planning, careful maxillary movement, and management of residual alveolar defects, scar-related tissue limitations, and relapse risk. Digital planning, three-dimensional imaging, computer-aided simulation, three-dimensional printed splints, and clear aligner systems were increasingly applied to improve diagnostic accuracy and surgical precision.
Conclusion: Orthodontic management for orthognathic surgery should be individualised according to skeletal pattern, dental compensation, cleft-related anatomical complexity, functional requirements, and patient-centred outcomes. Further prospective studies with standardised protocols and long-term follow-up are required to strengthen comparative evidence.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0021
- Title
- Proactive Management for Collaborative Cleft Lip and Cleft Palate Care in Upper Northern Part of Thailand
- Author(s)
- Supaksiri Suwiwattana
- Affiliation
- Princess Sirindhorn IT Foundation Craniofacial Center Chiang Mai University
Proactive Management for Collaborative Cleft Lip and Cleft Palate Care in Upper Northern Part of Thailand CP-0021
Supaksiri Suwiwattana · Case Study
Introduction
Proactive Management for Collaborative Cleft Lip and Cleft Palate Care in Upper Northern Part of Thailand is a system innovation addressing fragmentation in Thailand’s cleft care. It links university hospitals, Ministry of Public Health hospitals, and community networks into one coordinated, patient-centered system, ensuring continuous care from birth through early adulthood.
Essence of Innovation:
The new data-driven workflow eliminates fragmented care. Built on Chiang Mai University’s multidisciplinary expertise (Medicine, Dentistry, Associated Medical Sciences, Engineer, Information Technology Service Center, and Craniofacial Center), it closes workflow gaps. This collaboration combines network databases with the ThaiCleftLink program to streamline operations, empowering 38 hospitals across 8 northern provinces with standardized care, becomes model for expansion across Southeast Asia. The concept of this innovation system aligns with CMU’s core mission and vision as Thailand’s first regional university, advancing local and national development while supporting its current strategic objectives.
Starting Point:
Began as a CMU multidisciplinary collaboration, then scaled to a regional network linking university, Ministry of Public Health hospitals, and primary care units.
Steps Taken:
Phase 1: Collaborative Network – Established a common vision for coordinated care.
Phase 2: Centralized Data System – Developed the unified ThaiCleftLink platform for patient tracking.
Phase 3: Proactive Management – Conducted a gap analysis, then introduced rotating surgical teams, speech therapy, integrated dental care, telemedicine, and referral systems, dramatically reducing loss-to-follow-up.
Resources Used:
Backed by Chiang Mai University's president, SCFC, and a Ministry of Public Health partnership. Chiang Mai University provided academic/technical expertise, health offices provided personnel, and ITSC provided IT infrastructure.
Impact:
Financial: Patient travel expenses dropped by ~17%. Social/Health Equity: The program supports 2,873 patients via 57 hospitals, and 546 professionals. With the Social Return on Investment (SROI) ratio of 6.28:1, demonstrating high social/economic value.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0023
- Title
- Simultaneous Fronto-Orbital Advancement and Le Fort III Distraction in Saethre–Chotzen Syndrome Initially Suspected of Having Carpenter Syndrome
- Author(s)
- Kahoko Yamada
- Affiliation
- Department of Plastic, Reconstructive, and Aesthetic Surgery, Graduate School of Medicine, Chiba University, Chiba, Japan
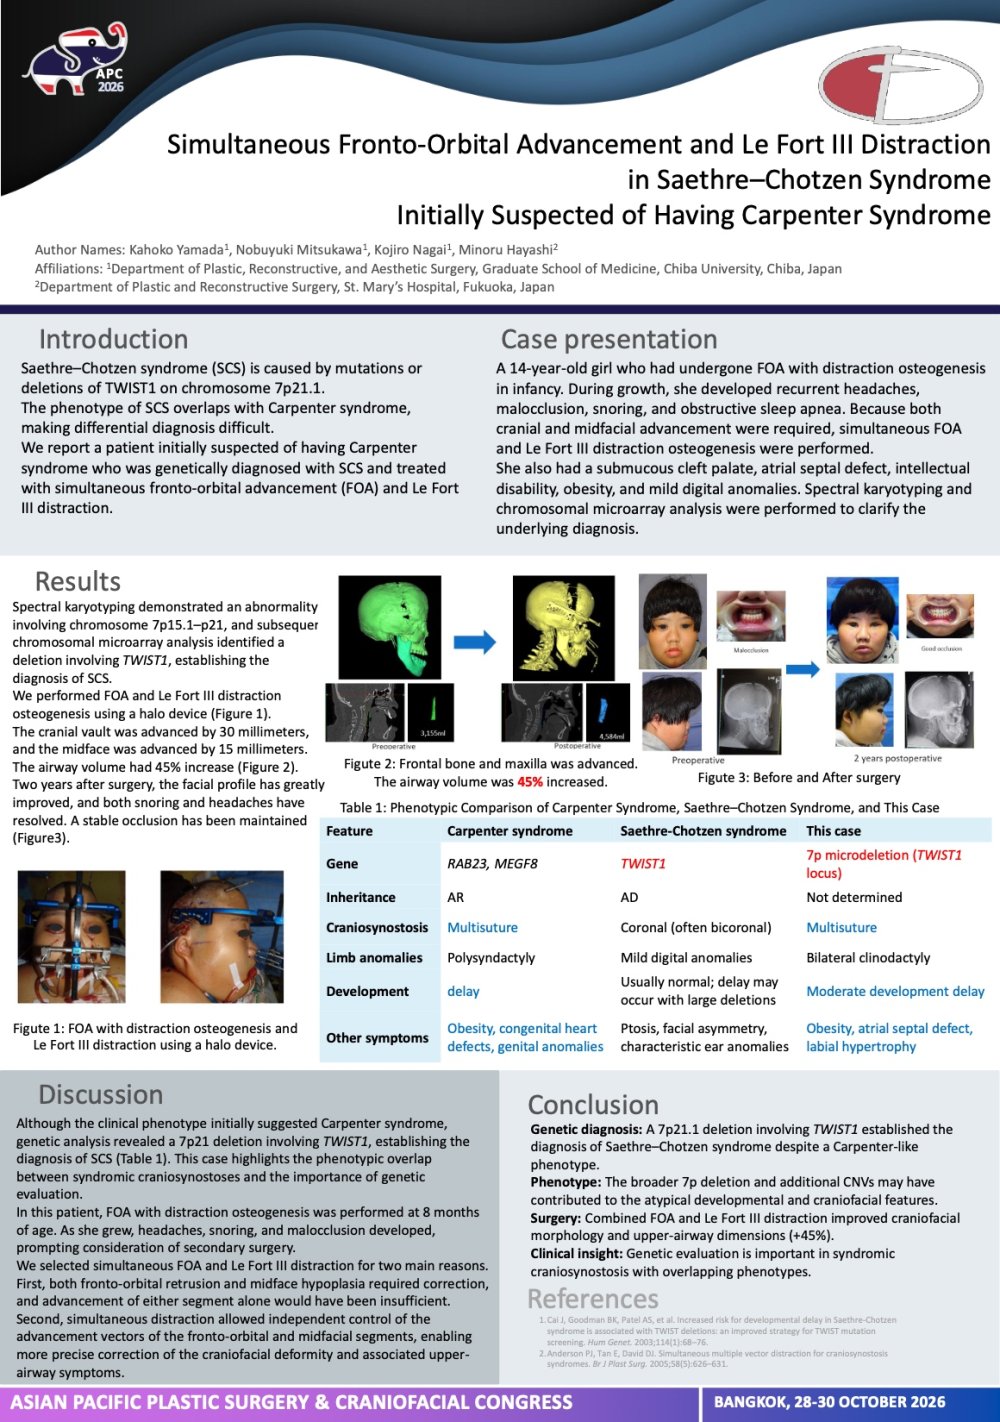
Simultaneous Fronto-Orbital Advancement and Le Fort III Distraction in Saethre–Chotzen Syndrome Initially Suspected of Having Carpenter Syndrome CP-0023
Kahoko Yamada · Case Study
Introduction:
Saethre–Chotzen syndrome is a TWIST1-related craniosynostosis with variable craniofacial and digital manifestations. Phenotypic overlap with other syndromic craniosynostoses may complicate clinical diagnosis. We report a patient initially suspected of having Carpenter syndrome who was genetically diagnosed with Saethre–Chotzen syndrome and treated with simultaneous fronto-orbital advancement and Le Fort III distraction.
Materials & Methods:
We retrospectively reviewed the clinical course of a 14-year-old girl who had undergone fronto-orbital advancement with distraction osteogenesis in infancy. During growth, she developed recurrent headaches, malocclusion, snoring, and obstructive sleep apnea. Because both cranial and midfacial advancement were required, simultaneous fronto-orbital advancement and Le Fort III distraction osteogenesis were performed to allow independent control of the advancement distances and vectors. She also had a submucous cleft palate, atrial septal defect, intellectual disability, obesity, and mild digital anomalies. Spectral karyotyping and chromosomal microarray analysis were performed to clarify the underlying diagnosis.
Results:
The cranial vault and midface were advanced by 30 mm and 15 mm, respectively. Postoperatively, facial profile and occlusion improved, snoring resolved, and recurrent headaches disappeared. These improvements were maintained at 2-year follow-up. Spectral karyotyping demonstrated an abnormality involving chromosome 7p15.1–p21, and subsequent chromosomal microarray analysis identified a deletion involving TWIST1, establishing the diagnosis of Saethre–Chotzen syndrome.
Conclusion:
Simultaneous fronto-orbital advancement and Le Fort III distraction allowed separate control of cranial and midfacial advancement and achieved stable functional and aesthetic improvement. Genetic testing subsequently clarified the diagnosis as Saethre–Chotzen syndrome in this patient with an atypical craniosynostosis phenotype.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0027
- Title
- Three-Dimensional Assessment of Upper Airway Changes After Mandibular Distraction Osteogenesis in Patients With Severe Micrognathia
- Author(s)
- Kahoko Yamada
- Affiliation
- Department of Plastic, Reconstructive, and Aesthetic Surgery, Graduate School of Medicine, Chiba University, Chiba, Japan
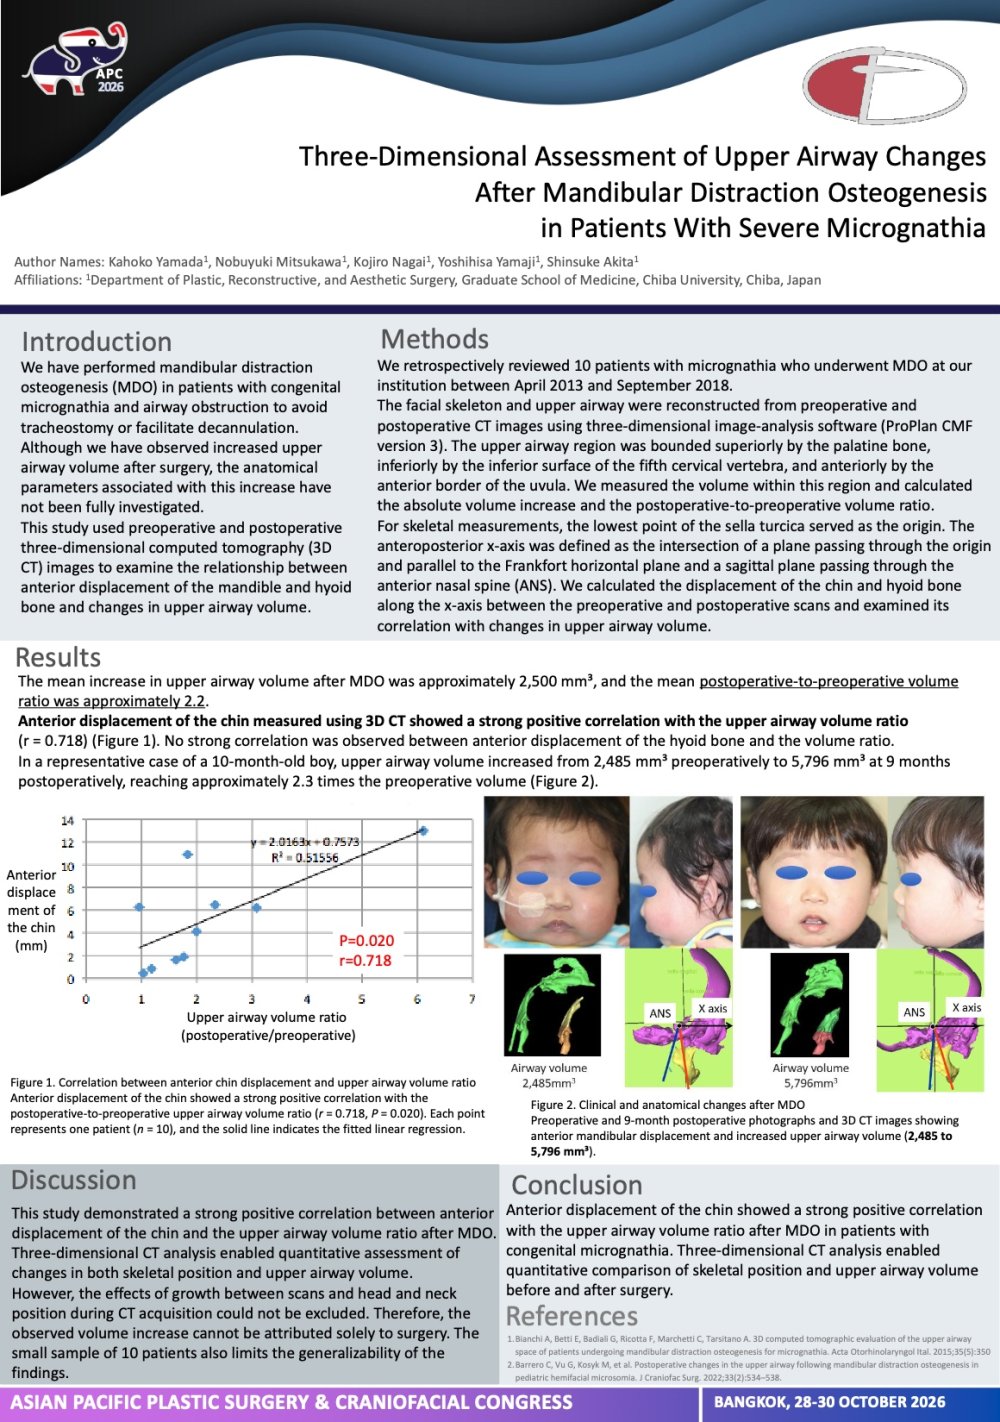
Three-Dimensional Assessment of Upper Airway Changes After Mandibular Distraction Osteogenesis in Patients With Severe Micrognathia RP-0027
Kahoko Yamada · Research
Introduction:
Congenital micrognathia may cause severe upper airway obstruction, and mandibular distraction osteogenesis can facilitate tracheostomy avoidance or decannulation. However, the anatomical changes associated with postoperative airway enlargement remain incompletely understood. This study evaluated upper airway volume before and after mandibular distraction osteogenesis using three-dimensional computed tomography and examined its relationship with anterior displacement of the chin and hyoid bone.
Materials & Methods:
We retrospectively reviewed 10 patients with congenital micrognathia who underwent mandibular distraction osteogenesis at our institution between April 2013 and September 2018. Preoperative and postoperative computed tomography images were reconstructed using three-dimensional image-analysis software. Upper airway volume was calculated within a standardized region defined using the palatal plane, uvular tip, and inferior surface of the fifth cervical vertebra. A three-dimensional coordinate system based on the lowest point of the sella turcica and the Frankfort horizontal plane was used to measure anterior displacement of the chin and hyoid bone. Associations between these displacements and changes in upper airway volume were examined.
Results:
Upper airway volume increased overall after mandibular distraction osteogenesis. The mean absolute increase was approximately 2,500 mm³, and the mean postoperative-to-preoperative volume ratio was approximately 2.2. Anterior displacement of the chin measured by three-dimensional computed tomography showed a strong positive correlation with the proportional increase in upper airway volume (r = 0.718). Hyoid displacement varied considerably among patients and showed no strong correlation with airway volume change.
Conclusion:
Anterior displacement of the chin after mandibular distraction osteogenesis was associated with proportional enlargement of the upper airway. Three-dimensional computed tomography enables quantitative assessment of postoperative airway changes and may complement conventional cephalometric evaluation in patients with severe micrognathia.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0006
- Title
- A Novel Turn-Over Upper Helical Cartilage Flap Augmented with Ninth Costal Cartilage Graft for Type I Microtia Reconstruction: A Case Report
- Author(s)
- Fajar Sartika Hadi
- Affiliation
- Department of Plastic Reconstructive and Aesthetic Surgery, Faculty of Medicine, Universitas Airlangga; Plastic Reconstructive and Aesthetic Surgery Unit, Universitas Airlangga Hospital
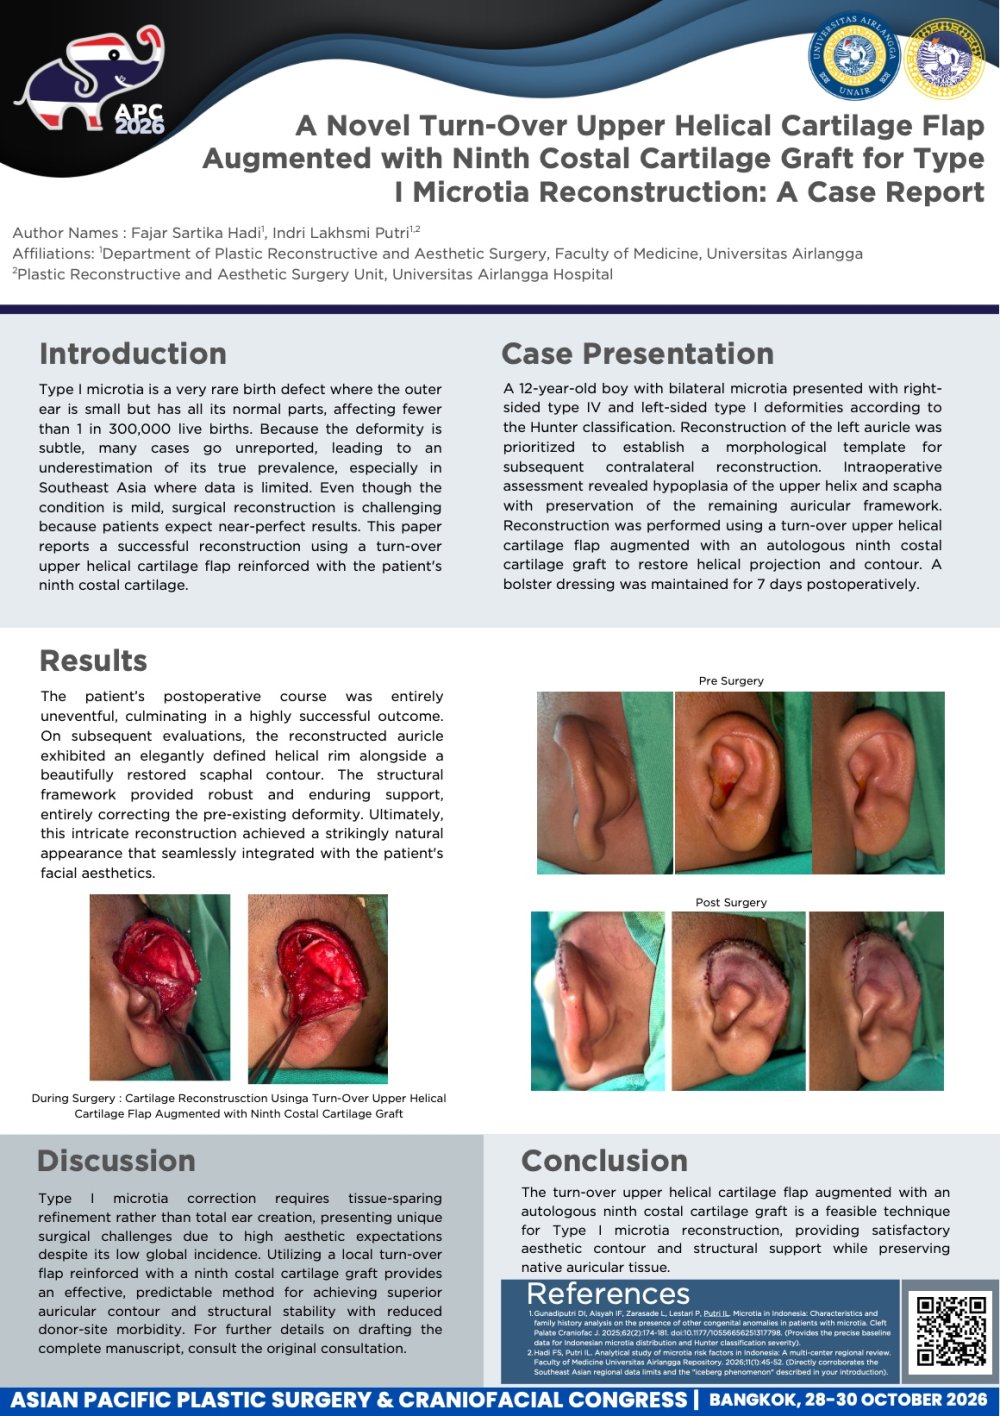
A Novel Turn-Over Upper Helical Cartilage Flap Augmented with Ninth Costal Cartilage Graft for Type I Microtia Reconstruction: A Case Report CP-0006
Fajar Sartika Hadi · Case Study
Introduction: Type I microtia is an exceedingly rare congenital auricular anomaly characterized by a hypoplastic auricle with preservation of all anatomical components, with an estimated incidence of fewer than 1 in 300,000 live births. Epidemiological data from Southeast Asia remain limited, restricting accurate assessment of its prevalence in this region. The low reported incidence may reflect the subtle nature of the deformity, which is often unrecognized or not considered severe enough to warrant medical attention, resulting in an iceberg phenomenon where the true disease burden is likely underestimated. Despite its mild external appearance, surgical correction presents unique challenges, as patients seeking reconstruction often have high expectations for achieving a near-normal auricular appearance. We report a case of Type I microtia reconstructed using a turn-over upper helical cartilage flap augmented with an autologous ninth costal cartilage graft.
Case Presentation: A 12-year-old boy with bilateral microtia presented with right-sided type IV and left-sided type I deformities according to the Hunter classification. Reconstruction of the left auricle was prioritized to establish a morphological template for subsequent contralateral reconstruction. Intraoperative assessment revealed hypoplasia of the upper helix and scapha with preservation of the remaining auricular framework. Reconstruction was performed using a turn-over upper helical cartilage flap augmented with an autologous ninth costal cartilage graft to restore helical projection and contour. A bolster dressing was maintained for 7 days postoperatively.
Results : The postoperative course was uneventful, the reconstructed auricle demonstrated a well-defined helical rim, improved scaphal contour, satisfactory structural support, and resulting in a more natural auricular appearance compared with the preoperative deformity.
Conclusion : The turn-over upper helical cartilage flap augmented with an autologous ninth costal cartilage graft is a feasible technique for Type I microtia reconstruction, providing satisfactory aesthetic contour and structural support while preserving native auricular tissue.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0034
- Title
- Evaluation of Alveolar Bone Formation Following Primary Gingivoperiosteoplasty in Patients With Unilateral Complete Cleft Lip and Palate
- Author(s)
- Madoka Sugiyama
- Affiliation
- Department of Plastic and Reconstructive Surgery, Kanagawa Children's Medical Center, Yokohama, Japan
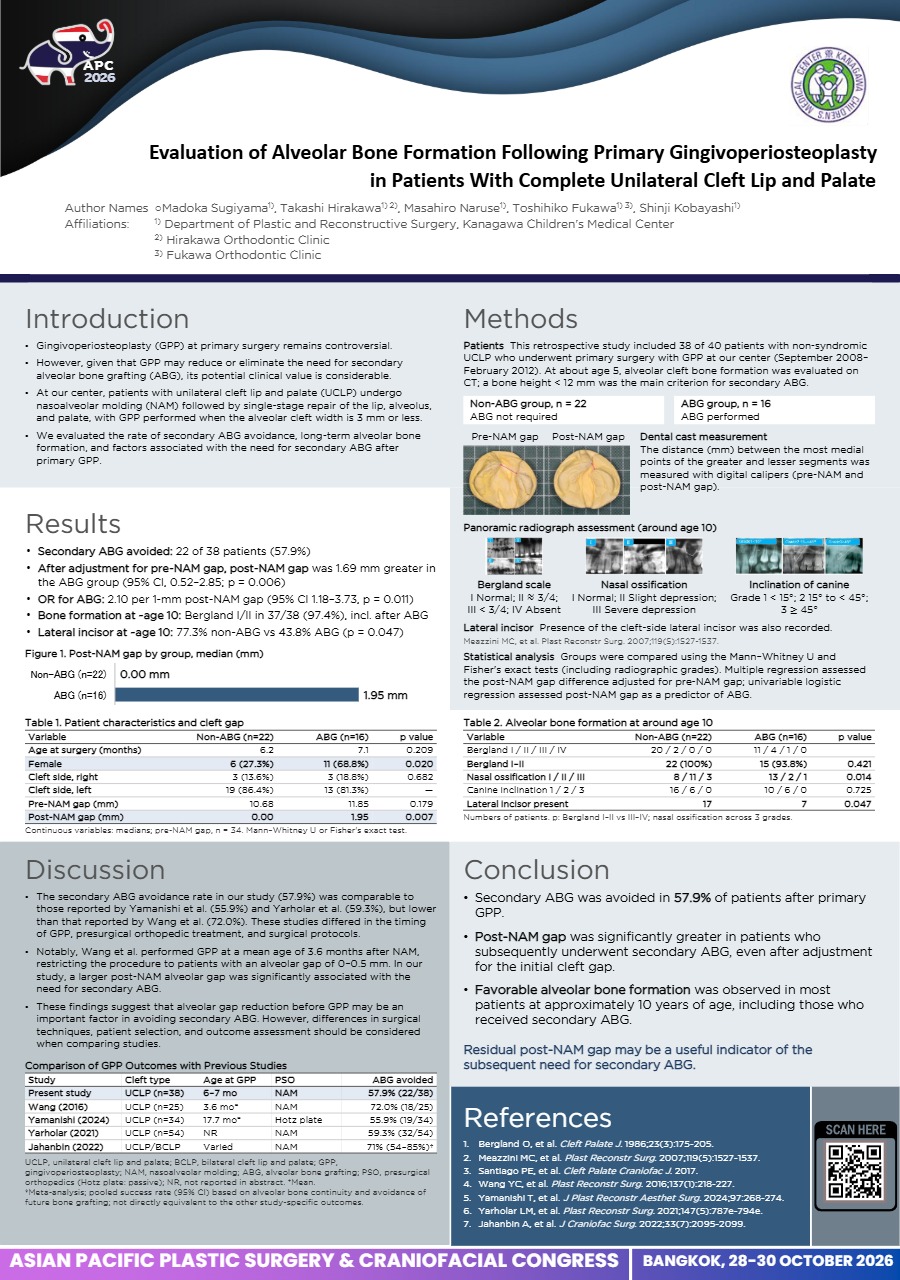
Evaluation of Alveolar Bone Formation Following Primary Gingivoperiosteoplasty in Patients With Unilateral Complete Cleft Lip and Palate RP-0034
Madoka Sugiyama · Research
Evaluation of Alveolar Bone Formation Following Primary Gingivoperiosteoplasty in Patients With Unilateral Complete Cleft Lip and Palate
Introduction:
At our center, patients with unilateral complete cleft lip and palate (UCLP) undergo presurgical orthopedics followed by simultaneous primary repair of the lip, alveolus, and palate. Although the role of gingivoperiosteoplasty (GPP) at primary repair remains controversial, successful bone formation may reduce the need for secondary alveolar bone grafting (ABG). This study evaluated alveolar bone formation following primary GPP and the subsequent need for secondary ABG.
Methods:
Forty patients with nonsyndromic UCLP who underwent primary surgery between September 2008 and February 2012 were retrospectively reviewed. The need for secondary ABG was assessed, and alveolar bone formation was evaluated on panoramic radiographs using the Bergland classification.
Results:
Thirty-eight of 40 patients (95.0%) underwent GPP during primary repair. Of these, 22 (57.9%) achieved sufficient alveolar bone formation without secondary ABG, whereas 16 (42.1%) subsequently underwent ABG at a mean age of 6.4 ± 0.7 years. In the non-ABG group, the Bergland classification was type I in 20 patients and type II in 2. In the ABG group, the final classification was type I in 11 patients, type II in 4, and type III in 1. No patient required repeat bone grafting.
Conclusion:
Primary GPP performed with simultaneous lip, alveolar, and palate repair avoided secondary ABG in 57.9% of patients with UCLP. These findings suggest that GPP may reduce the need for secondary bone grafting. Further three-dimensional imaging studies are needed to more accurately characterize alveolar bone formation following GPP
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0033
- Title
- A Patient of True Median Cleft Lip with Unilateral Anophthalmia and Morning Glory Syndrome
- Author(s)
- Nobuyuki Mitsukawa
- Affiliation
- Department of Plastic, Reconstructive, and Aesthetic Surgery, Chiba University Graduate School of Medicine
A Patient of True Median Cleft Lip with Unilateral Anophthalmia and Morning Glory Syndrome CP-0033
Nobuyuki Mitsukawa · Case Study
Objective:
Median cleft lip is an extremely rare condition, accounting for approximately 0.1–0.7% of cleft lip and palate cases. We report a case of true median cleft lip associated with unilateral anophthalmia and morning glory syndrome.
Case Report:
A male infant weighing 2608 g was born at 37 weeks and 1 day of gestation via normal delivery from a GBS-positive mother. At birth, a fissure was observed in the midline of the upper lip and alveolar ridge, along with a bilobed protuberant lesion in the alveolar cleft region. No brain malformations were detected, and a bifid frenulum was present, confirming the diagnosis of true median cleft lip. Additionally, the patient had right-sided morning glory syndrome and left-sided anophthalmia.
Results:
At six months of age, the patient underwent primary closure of the cleft, wedge excision at the nasal base, and resection of the protuberant lesion in the alveolar cleft region. Histopathological examination revealed that the lesion primarily consisted of immature cartilage-like tissue with vascular proliferation, suggesting a hamartoma caused by heterotopic jawbone-derived tissue. The postoperative course was uneventful, and at two years post-surgery, the patient maintains a favorable lip morphology.
Discussion:
Median cleft lip can be classified into true median cleft lip, characterized by a fissure separating the tissues, and pseudo-median cleft lip, which results from hypoplasia of the midfacial structures. True median cleft lip is attributed to failure of fusion of the medial nasal prominences between the 5th and 8th weeks of gestation. The severity of the cleft varies from a minor notch in the vermilion to involvement of the external nose and mandible. Since this condition is not typically associated with brain malformations or growth impairments, the prognosis is generally favorable.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0030
- Title
- First Successful Le Fort III Distraction in a Patient with Beare-Stevenson Syndrome
- Author(s)
- Nobuyuki Mitsukawa
- Affiliation
- 1) Department of Plastic, Reconstructive, and Aesthetic Surgery, Graduate School of Medicine, Chiba University
First Successful Le Fort III Distraction in a Patient with Beare-Stevenson Syndrome CP-0030
Nobuyuki Mitsukawa · Case Study
Objective: Beare-Stevenson syndrome is a genetic disorder, caused by FGFR2 gene mutations, characterized by craniosynostosis, midface hypoplasia, Chiari malformation, and other extensive congenital abnormalities. We performed Le Fort III distraction osteogenesis on a girl with this condition and achieved favorable outcomes. This report describes the world's first successful Le Fort III distraction for a patient with Bear-Stevenson syndrome.
Methods: The patient is a 5-year-old girl. She was diagnosed with Beare-Stevenson syndrome shortly after birth and underwent a tracheostomy due to respiratory distress. At 2 month of age, a VP shunt placement was performed, followed by occipital cranial expansion at 1 year and fronto-orbital distraction at 2 years. She was referred to our department for treatment of midface hypoplasia. Clinical findings and imaging studies revealed severe proptosis, very severe midface hypoplasia, and reverse occlusion. We planned Le Fort III distraction using a halo-type external distraction device. Surgery was performed with utmost caution regarding the shunt tube and skull defects.
Results: Postoperatively, an approximately 25 mm distraction was achieved without major complications, 2 years after the operation, significant improvements in proptosis, occlusion, and facial profile were observed, with an excellent clinical course.
Discussion: Beare-Stevenson syndrome is an extremely rare condition presenting with severe midface hypoplasia, with only around 30 reported cases. Due to the poor prognosis associated with respiratory complications, this is, to our knowledge, this case represents the first successful report of Le Fort III distraction. Given the high incidence of Chiari malformations along with the characteristic craniofacial abnormalities, early intervention by both pediatric neurosurgeons and plastic surgeons is crucial. This syndrome presents with severe midface hypoplasia and is associated with poor prognosis due to respiratory complications. However, for cases considered to have a relatively favorable prognosis, Le Fort III distraction should be actively pursued.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0028
- Title
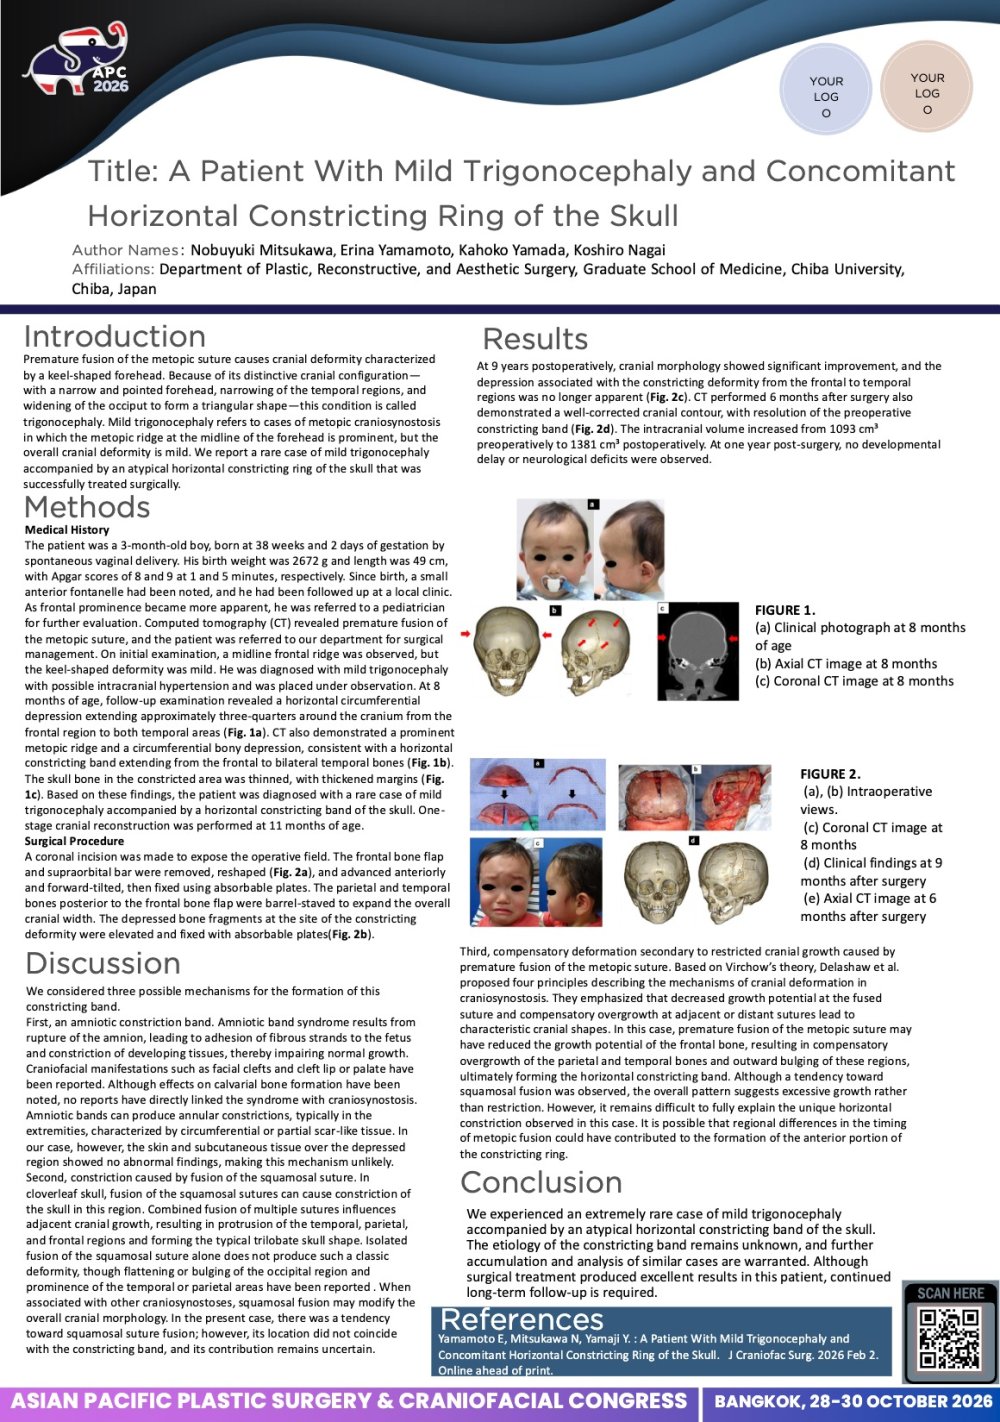
- A Patient With Mild Trigonocephaly and Concomitant Horizontal Constricting Ring of the Skull
- Author(s)
- Nobuyuki Mitsukawa
- Affiliation
- Department of Plastic, Reconstructive, and Aesthetic Surgery, Graduate School of Medicine, Chiba University
A Patient With Mild Trigonocephaly and Concomitant Horizontal Constricting Ring of the Skull CP-0028
Nobuyuki Mitsukawa · Case Study
Introduction:
Metopic craniosynostosis causes characteristic cranial deformities such as a keel-shaped forehead, known as trigonocephaly. Mild trigonocephaly refers to cases of metopic craniosynostosis in which the cranial deformity is generally mild. We report a case of mild trigonocephaly accompanied by an atypical horizontal constricting ring of the skull that was successfully treated surgically.
Case Report:
The patient was a 3-month-old boy. CT revealed premature fusion of the metopic suture, and he was referred to our department for surgical treatment. A midline frontal ridge was observed but the keel-shaped forehead was not prominent, and the patient was diagnosed with mild trigonocephaly. Mild depression was observed in the temporal regions, and CT demonstrated a horizontal constricting ring of the skull (circumferential depression) extending approximately three-quarters of the way from the frontal region to both temporal areas. At 11 months of age, one-stage cranial reconstruction was performed for mild trigonocephaly, along with correction of the constricting deformity. Through a coronal incision, the supraorbital bar and frontal bone flap were removed and reshaped. The parietal and temporal bones posterior to the frontal bone flap were barrel-staved, and the depressed bone fragments were elevated to reconstruct the constricted region. Postoperatively, the frontal contour improved, and the constricting ring observed before surgery resolved, resulting in an overall satisfactory cranial shape. One year after surgery, no signs of developmental delay or neurological impairment were observed.
Conclusion:
Cases of nonsyndromic craniosynostosis with a horizontal constricting ring are extremely rare, and to our knowledge, none have been previously reported. Possible etiologies include an amniotic constriction band, a constricting ring caused by squamosal suture fusion as seen in cloverleaf skull, or compensatory deformation associated with restricted cranial growth; however, the exact mechanism remains unclear.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
CP-0008
- Title
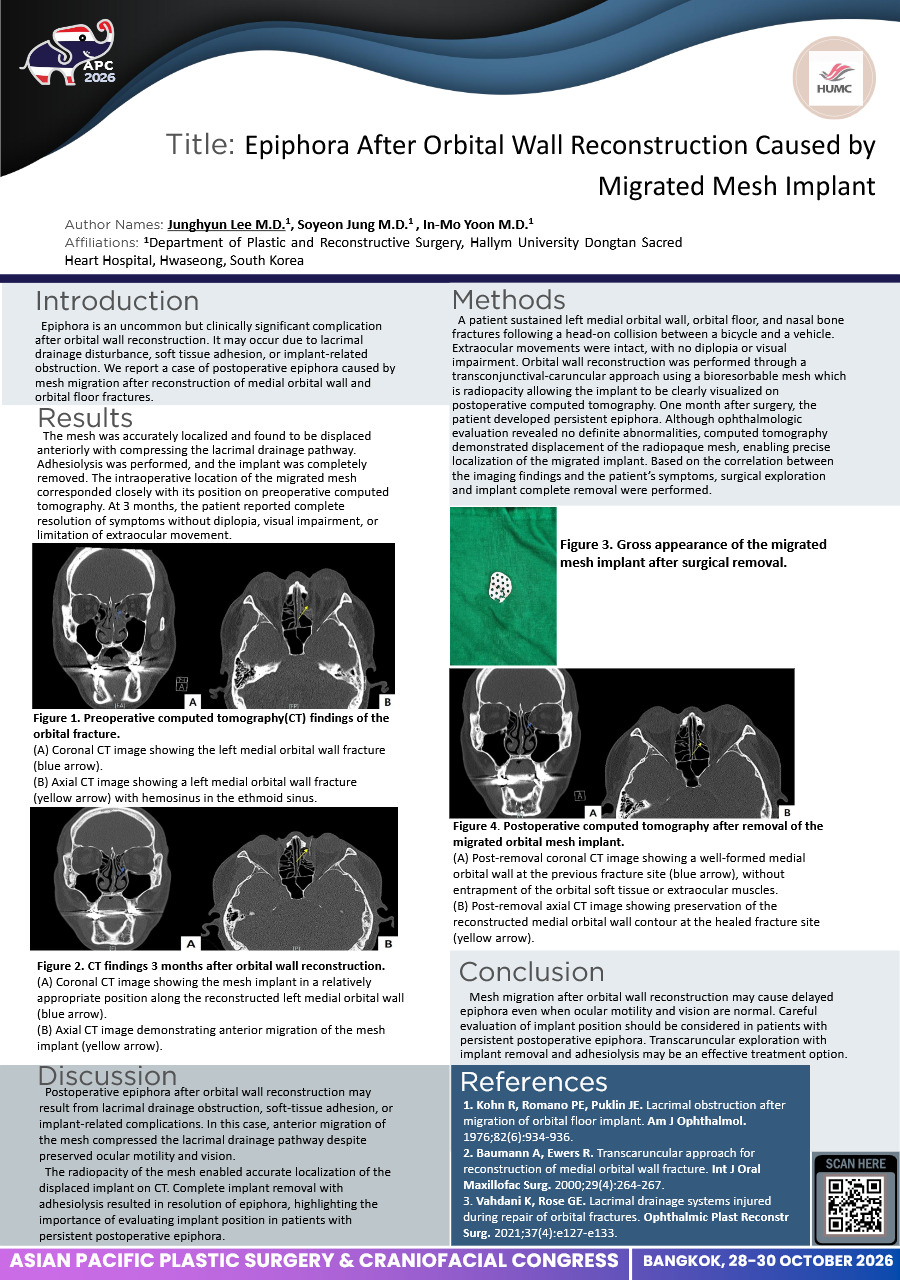
- Epiphora After Orbital Wall Reconstruction Caused by Migrated Mesh Implant
- Author(s)
- Junghyun Lee
- Affiliation
- Department of Plastic and Reconstructive Surgery, Hallym University Dongtan Sacred Heart Hospital, Hwaseong, Korea
Epiphora After Orbital Wall Reconstruction Caused by Migrated Mesh Implant CP-0008
Junghyun Lee · Case Study
Introduction: Epiphora is an uncommon but clinically significant complication after orbital wall reconstruction. It may occur due to lacrimal drainage disturbance, soft tissue adhesion, or implant-related obstruction. We report a case of postoperative epiphora caused by mesh migration after reconstruction of medial orbital wall and orbital floor fractures.
Methods: A patient sustained left medial orbital wall, orbital floor, and nasal bone fractures following a head-on collision between a bicycle and a vehicle. Extraocular movements were intact, with no diplopia or visual impairment. Orbital wall reconstruction was performed through a transconjunctival-caruncular approach using a bioresorbable mesh which is radiopacity allowing the implant to be clearly visualized on postoperative computed tomography. One month after surgery, the patient developed persistent epiphora. Although ophthalmologic evaluation revealed no definite abnormalities, computed tomography demonstrated displacement of the radiopaque mesh, enabling precise localization of the migrated implant. Based on the correlation between the imaging findings and the patient’s symptoms, surgical exploration and implant complete removal were performed.
Results: The mesh was accurately localized and found to be displaced anteriorly with compressing the lacrimal drainage pathway. Adhesiolysis was performed, and the implant was completely removed. The intraoperative location of the migrated mesh corresponded closely with its position on preoperative computed tomography. At 3 months, the patient reported complete resolution of symptoms without diplopia, visual impairment, or limitation of extraocular movement.
Conclusion: Mesh migration after orbital wall reconstruction may cause delayed epiphora even when ocular motility and vision are normal. Careful evaluation of implant position should be considered in patients with persistent postoperative epiphora. Transcaruncular exploration with implant removal and adhesiolysis may be an effective treatment option.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
RP-0011
- Title
- Reconstruction with bilateral hatchet flaps for medium sized scalp defects.
- Author(s)
- Junghyun Lee
- Affiliation
- Department of Plastic and Reconstructive Surgery, Hallym University Dongtan Sacred Heart Hospital, Hwaseong, Korea
Reconstruction with bilateral hatchet flaps for medium sized scalp defects. RP-0011
Junghyun Lee · Research
Introduction: Reconstruction of scalp defects is challenging because of the convex contour, hair-bearing skin, and need for durable calvarial coverage. The hatchet flap combines advancement and rotation, redistributes tension, and preserves adjacent hair-bearing tissue. This study evaluated the clinical utility and surgeon-assessed outcomes of hatchet flap reconstruction for medium-sized scalp defects after excision of benign or malignant lesions.
Methods: We retrospectively reviewed 18 patients who underwent hatchet flap-based scalp reconstruction between March 2024 and 2026. Indications included skin cancer, soft-tissue mass, nevus sebaceous, seborrheic keratosis, epidermal cyst, infected cystic mass, and scalp skin necrosis. After excision or debridement, primary closure was not feasible because of defect size, location, or closure tension. Flaps were designed according to defect location and surrounding tissue mobility. Postoperative flap viability, wound complications, revision surgery, hair-bearing appearance, aesthetic outcomes, and local symptoms were reviewed.
Results: Defects involved the scalp, occiput, vertex, or temple. All patients achieved successful wound closure. No total or partial flap necrosis occurred, and no patient required reoperation or secondary reconstruction. The operating surgeon assessed postoperative contour, tissue match, and preservation of hair-bearing scalp as satisfactory. Pain, pruritus, and other local discomfort were minimal or tolerable during follow-up.
Conclusion: Hatchet flap-based reconstruction is a reliable and versatile option for scalp defects that cannot be closed primarily. It provides durable coverage, favorable tissue matching, preservation of hair-bearing scalp, and satisfactory surgeon-assessed aesthetic outcomes. Longer follow-up is required to evaluate scar maturation, alopecia, long-term aesthetic results, and symptom changes.
View only · Double-click poster to enlarge · Download & print disabled
Loading poster…
Page 2 of 4 (45 poster(s))
Double-click or press Esc to close · Scroll to zoom